
Tapentadol Side Effects & GI Tolerability: Constipation Rates, Nausea Management, and CNS Drowsiness

Tapentadol Side Effects & GI Tolerability: Constipation Rates, Nausea Management, and CNS Drowsiness
A comprehensive clinical review of tapentadol adverse effects, focusing on its favorable gastrointestinal profile, lower constipation incidence compared to classic opioids, and nausea management.
CLINICAL SAFETY REVIEW
EXECUTIVE CLINICAL SUMMARY
Tapentadol is clinically distinguished by a significantly lower burden of gastrointestinal side effects compared to traditional equianalgesic doses of classical opioids like oxycodone and morphine. Because up to 50% of tapentadol’s antinociceptive potency is derived from norepinephrine reuptake inhibition rather than pure μ-opioid receptor agonism, it induces approximately 50% to 60% less bowel dysfunction (opioid-induced constipation). Nonetheless, common central adverse effects including nausea, somnolence, dizziness, and headache require systematic clinical management.
01. Gastrointestinal tolerability: Reduced constipation incidence compared to classic opioids
Opioid-induced constipation (OIC) represents the most persistent and debilitating side effect of chronic pain pharmacotherapy, mediated by peripheral μ-opioid receptors in the myenteric and submucosal plexuses of the intestinal wall. In clinical Phase III trials, chronic constipation occurred in only 8% to 12% of tapentadol-treated patients, compared to 26% to 34% of oxycodone-treated cohorts.
| ADVERSE EVENT | INCIDENCE (TAPENTADOL) | INCIDENCE (OXYCODONE) | PHYSIOLOGICAL MECHANISM | CLINICAL INTERVENTION |
|---|---|---|---|---|
| Nausea | 18% – 22% | 30% – 38% | Chemoreceptor trigger zone stimulation | Administer with meals; antiemetics PRN |
| Constipation | 8% – 12% | 26% – 34% | Enteric MOR activation, delayed transit | Dietary fiber, hydration, osmotic laxatives |
| Drowsiness / Somnolence | 15% – 20% | 25% – 30% | Central MOR sedation, cortical calming | Avoid evening titration; clear morning tasks |
| Dizziness / Vertigo | 10% – 14% | 16% – 22% | Vestibular sensitivity, mild orthostasis | Sit-to-stand transitions, slow mobility |
| Pruritus (Itching) | 4% – 6% | 12% – 18% | Central pruriceptive pathway signaling | Oral non-sedating antihistamines PRN |
02. Nausea and emesis management during initial dose titration
Nausea is most frequent during the first 3 to 5 days of initiating tapentadol therapy. It arises from stimulation of the chemoreceptor trigger zone (CTZ) in the area postrema. Taking tablets with light snacks and remaining recumbent for 30 minutes following initial doses minimizes vestibular exacerbation. If needed, short-term ondansetron or promethazine may be utilized.
03. Central nervous system sedation, psychomotor impairment, and driving safety
Somnolence and mild cognitive slowing are dose-dependent effects that typically attenuate as pharmacodynamic tolerance develops over 5 to 7 days. Patients must be explicitly advised to refrain from operating motor vehicles, operating power machinery, or engaging in safety-critical professional activities until their stable maintenance dosage is achieved without daytime sedation.
04. Cardiovascular parameters: Heart rate, blood pressure, and orthostasis
Due to its noradrenergic activity, tapentadol does not cause significant orthostatic hypotension or bradycardia in the manner of classic vasodilatory opioids. However, mild transient elevations in blood pressure can occasionally occur in patients with pre-existing untreated hypertension; baseline vitals should be documented.
05. Rare but serious adverse reactions: Respiratory depression and allergic hypersensitivity
Although rare at therapeutic doses, life-threatening respiratory depression can occur in patients with undiagnosed obstructive sleep apnea, severe chronic obstructive pulmonary disease (COPD), or those co-ingesting sedatives. Any manifestation of cyanosis, shallow breathing (<10 breaths/min), or extreme lethargy requires urgent emergency medical care.
06. Detailed Receptor Neurobiology & Dual-Mechanism Pain Pathway Pharmacology
Unlike classical pure μ-opioid receptor agonists, Tapentadol exhibits an innovative dual synergistic mechanism of action designed to attenuate both ascending nociceptive signals and augment descending inhibitory pain pathways within the central nervous system:
First, it binds directly to the μ-opioid receptor (MOR) located on presynaptic primary afferent neurons in the dorsal horn substantia gelatinosa and periaqueductal gray (PAG). Receptor coupling to inhibitory Gi/o proteins inhibits adenylate cyclase, reduces intracellular cyclic AMP, closes voltage-gated N-type calcium channels, and stimulates inward-rectifying potassium conductance. This presynaptic hyperpolarization directly suppresses the release of excitatory nociceptive neurotransmitters, specifically substance P, glutamate, and calcitonin gene-related peptide (CGRP).
Second, Tapentadol produces potent monoamine reuptake inhibition. By blocking the norepinephrine transporter (NET), it substantially increases synaptic concentrations of norepinephrine in descending bulbospinal inhibitory tracts. Synaptic norepinephrine stimulates post-junctional α2-adrenergic receptors on secondary spinal projection neurons, evoking hyperpolarization that blocks dorsal horn nociceptive transmission.
| PHARMACOLOGICAL TARGET | NEUROANATOMICAL SITE | MOLECULAR MECHANISM | CLINICAL ANALGESIC MANIFESTATION |
|---|---|---|---|
| μ-Opioid Receptor (MOR) | Dorsal horn substantia gelatinosa, periaqueductal gray | Gi/o-protein coupling, calcium channel blockade | Immediate suppression of acute nociceptive pain and visceral trauma |
| Norepinephrine Transporter (NET) | Descending bulbospinal tract, locus coeruleus projections | Neuronal reuptake inhibition, elevated synaptic NE | Potent relief of chronic neuropathic, radicular, and central sensitization pain |
| α2-Adrenoceptor Agonism | Dorsal horn interneurons and second-order projection neurons | Spinal inhibitory hyperpolarization | Synergistic opioid-sparing effect, enabling lower therapeutic doses |
| Mu-Opioid Spare Fraction | Intrinsic spinal antinociceptive circuit | Balanced dual-action synergy | Markedly lower GI adverse burden compared to classical opioids |
Because the noradrenergic component contributes up to 50% of the total analgesic efficacy, Tapentadol requires significantly less μ-opioid receptor occupancy than traditional opioids to achieve equivalent analgesia. This molecular architecture results in a markedly superior gastrointestinal safety profile, characterized by reduced incidence of severe constipation, respiratory depression, and rapid tolerance development.
07. Hepatic Clearance, Renal Impairment & Beers Criteria Safety
Safe clinical application of Tapentadol demands precise evaluation of metabolic pathways and organ clearance kinetics. Unlike many conventional medications, elimination characteristics differ significantly across patient populations:
| CLINICAL SUBGROUP | PHARMACOKINETIC KINETICS | DOSING MODIFICATION PROTOCOL | SAFETY / MONITORING DIRECTIVE |
|---|---|---|---|
| Mild Hepatic Impairment (Child-Pugh A) | Slight clearance reduction, normal volume of distribution | Standard adult starting dose; titrate with conservative intervals | Monitor for augmented somnolence or dizziness |
| Moderate Hepatic Impairment (Child-Pugh B) | Systemic exposure (AUC) increased 2- to 3-fold | Extend dosing interval to every 8 to 12 hours; 50mg initial cap | Strict clinical observation; monitor transaminases |
| Severe Hepatic Impairment (Child-Pugh C) | Marked metabolic shunting, unpredictable elimination | Contraindicated; alternative analgesic pathways mandated | Risk of profound CNS sedation and drug accumulation |
| Renal Impairment (CrCl < 30 mL/min) | Impaired clearance of polar glucuronide or active metabolites | Extend dosing interval; avoid exceeding minimum therapeutic threshold | Monitor creatinine clearance and signs of cognitive blunting |
| Geriatric Patients (≥ 65 Years) | Decreased glomerular filtration, heightened CNS sensitivity | Initiate at the lowest manufactured strength (50mg / dose) | Fall precautions, orthostatic monitoring, Beers Criteria review |
Under the American Geriatrics Society (AGS) Beers Criteria®, central-acting analgesics require judicious prescriber oversight in older adults due to age-related declines in neuromuscular coordination, cognitive reserve, and renal clearance. Where indicated, starting doses must be conservative with scheduled safety checks.
08. Comprehensive Patient Clinical Safety & Dispensing Checklist
Before initiating therapy or taking each scheduled dose of Tapentadol, patients, caregivers, and clinical teams must review this standardized clinical verification checklist to prevent adverse drug events and dangerous drug-drug interactions:
PATIENT PRE-ADMINISTRATION SAFETY CRITERIA
- Alcohol Abstinence Verification: Strict zero-tolerance for ethanol ingestion. Combining alcohol with central-acting analgesics causes synergistic CNS and respiratory depression, which can be fatal.
- Concurrent CNS Depressant & Benzodiazepine Screen: Ensure no simultaneous dosing with sedatives, tranquilizers, or sleep aids unless specifically managed under multi-specialist clinical oversight.
- Serotonergic Agent Co-Prescription Assessment: Confirm patient is not concurrently taking MAO inhibitors (contraindicated within 14 days), high-dose SSRIs, SNRIs, or triptans to prevent the development of life-threatening Serotonin Syndrome.
- Respiratory & Bronchial Function Evaluation: Withhold administration if patient exhibits acute severe asthma, hypercapnia, or respiratory compromise in unmonitored settings.
- Seizure History & Threshold Assessment: Screen for past epileptic episodes or concomitant medications that lower seizure threshold (especially relevant for monoamine-active analgesics).
- Locked Storage & Secure Disposal: Maintain medication in its original child-resistant blister packaging within a locked lockbox at controlled room temperature (20°C to 25°C / 68°F to 77°F). Never store in bathroom medicine cabinets where humidity fluctuates.
09. Verified Pharmaceutical Formulations & Prescribing Profiles

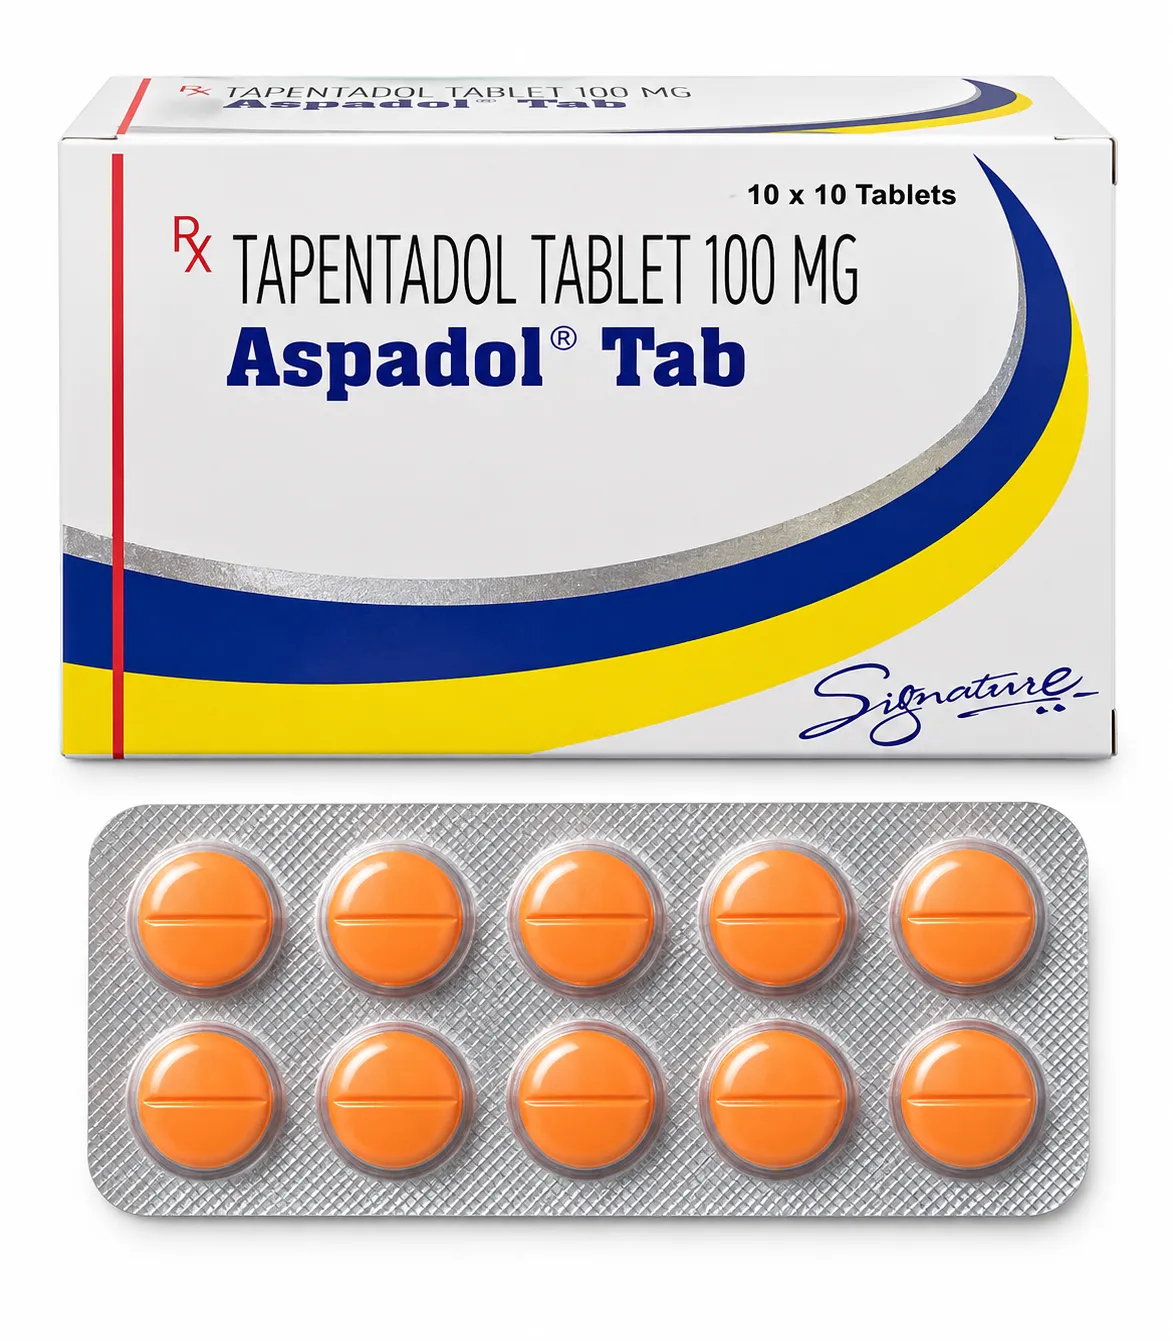
Aspadol 100mg (Tapentadol)
Dual-action centrally acting analgesic combining μ-opioid receptor agonism with norepinephrine reuptake inhibition for severe acute and neuropathic pain management.
10. Frequently Asked Questions
Why does tapentadol cause less constipation than other painkillers?
Tapentadol relies on norepinephrine reuptake inhibition for approximately half of its painkilling potency, meaning it occupies fewer μ-opioid receptors in the intestines, preserving normal bowel motility.
How can I stop feeling nauseous when starting tapentadol?
Take your dose with food or a glass of milk, stay seated or resting for 30 minutes after taking the tablet, and stay well hydrated. Nausea typically resolves after the first 3 to 5 days.
Does tapentadol cause itching or allergic hives?
Tapentadol causes far less histamine release than morphine or codeine. Mild itching occurs in only 4-6% of patients and can be relieved with standard antihistamines if necessary.
Can I drive while taking daily tapentadol 100mg?
You should never drive when starting tapentadol or immediately after increasing the dose. Once you have been on a stable dose for at least a week and feel fully alert, you may resume normal driving under doctor guidance.
What should I do if tapentadol makes me feel excessively dizzy upon standing?
Rise slowly from lying or sitting positions to allow blood pressure to equilibrate. If severe dizziness or lightheadedness persists, have your doctor review your cardiovascular and fluid status.
11. Clinical References & Regulatory Sources
- Journal of Pain Research. Gastrointestinal tolerability of tapentadol: pooled analysis of phase III trials. Source Database.
- Pain Practice. Efficacy and safety of tapentadol in moderate to severe chronic pain states. Source Database.
- FDA CDER. Nucynta Post-Marketing Adverse Reaction Surveillance Data. Source Database.
Consult a Clinical Pharmacy Specialist
Have questions regarding Tapentadol dosing intervals, CYP enzyme interactions, or physician-guided discontinuation protocols? Connect with our licensed clinical pharmacy team for patient safety guidance.
Related Patient Services & Verified Care
Every prescription order is verified by a licensed pharmacist in strict adherence to FDA BeSafeRx protocols.