
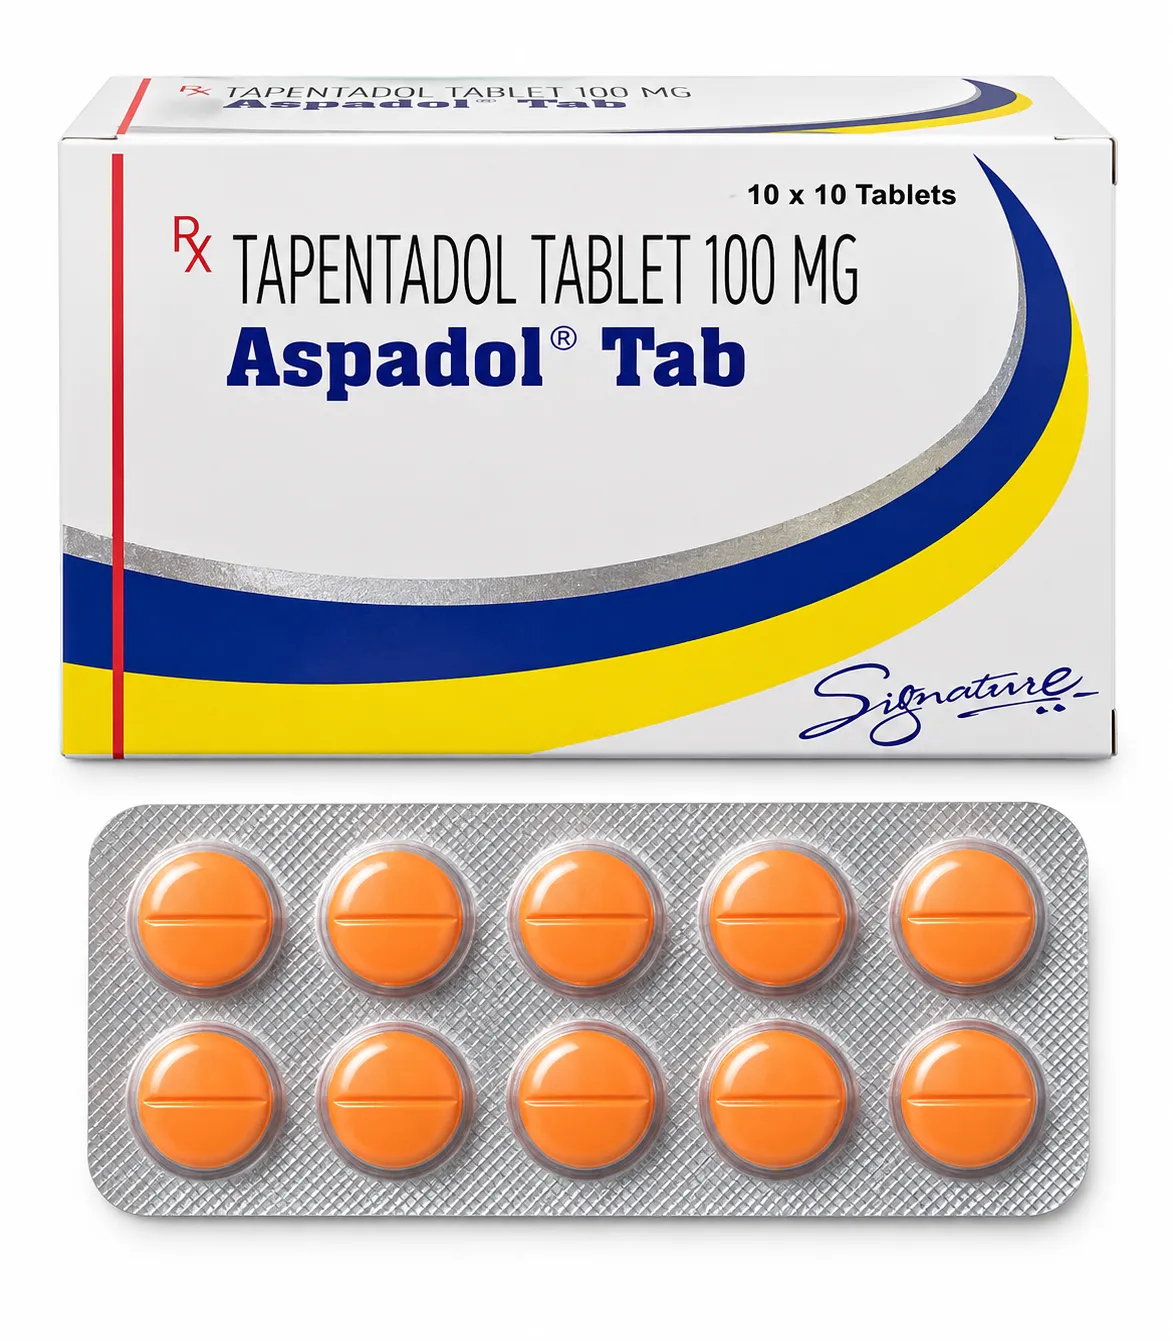
Aspadol & Tapentadol Pill Identifier: 100mg Markings, Blister Pack Verification, and Counterfeit Detection

Aspadol & Tapentadol Pill Identifier: 100mg Markings, Blister Pack Verification, and Counterfeit Detection
How to identify authentic Aspadol 100mg tablets, verify pharmaceutical blister packaging, inspect batch stamps, and prevent dangerous counterfeit exposure.
PHARMACEUTICAL IDENTIFIER
EXECUTIVE CLINICAL SUMMARY
Authentic Aspadol 100mg (Tapentadol Hydrochloride) is manufactured as a high-precision oral tablet designed for severe pain management. With the increasing prevalence of counterfeit analgesic tablets and illicit fentanyl adulteration across unauthorized online channels, patients and healthcare providers must verify physical tablet imprints, film coatings, uniform scoring, and tamper-evident pharmaceutical blister packaging before administration.
01. Visual tablet characteristics: Shape, scoring, color, and coating standards
Authentic pharmaceutical tapentadol tablets conform to rigorous Good Manufacturing Practice (GMP) pharmacopeial standards. Generic Aspadol 100mg is typically presented as a round, biconvex film-coated tablet with a uniform pale-orange to off-white appearance.
| STRENGTH / BRAND | PHYSICAL SHAPE | COLOR & COATING | IMPRINT CODES | PACKAGE FORMAT |
|---|---|---|---|---|
| Aspadol 100mg | Round, biconvex tablet | Pale orange / peach film coat | Deep functional bisect score / plain reverse | Tamper-evident 10-tablet blister strip |
| Nucynta 50mg | Round, film-coated | White to off-white | “O-M” on one side, “50” on reverse | Child-resistant HDPE bottle |
| Nucynta 100mg | Round, film-coated | Orange-yellow | “O-M” on one side, “100” on reverse | Child-resistant HDPE bottle |
| Suspect Counterfeit | Irregular, powdery tablet | Chalky, uneven coloring | Blurred numbers, chipped edges | Loose plastic baggies / unlabeled bottles |
02. Blister packaging security features and batch lot verification
Genuine Aspadol 100mg is dispensed exclusively in sealed push-through aluminium-PVC blister packaging. The backing foil must display razor-sharp pharmaceutical typography indicating the brand name “Aspadol 100”, active ingredient “Tapentadol HCl 100mg”, manufacturer details, lot number, manufacture date, and expiration date embossed directly into the edge crimping.
03. Chemical purity verification and excipient dissolution tests
Under USP dissolution testing, genuine tapentadol tablets release not less than 80% of active tapentadol hydrochloride into physiological gastric buffer (pH 1.2) within 30 minutes. Counterfeit formulations frequently exhibit irregular binders that either fail to dissolve or crumble rapidly into crumbly residue upon light tactile pressure.
04. Storage conditions and blister foil integrity maintenance
Tapentadol tablets must remain sealed in their protective blister cavities until immediately prior to dosing. Store at controlled room temperature between 20°C and 25°C (68°F to 77°F). Exposure to bathroom humidity or radiant heat can degrade the film coating and accelerate active ingredient hydrolytic decay.
05. Counterfeit warning signs: Fentanyl adulteration and red flags
Illicit counterfeit pressed tablets masquerading as tapentadol frequently contain lethal quantities of synthetic fentanyl or designer benzimidazoles. Severe red flags include tablets that crumble easily, have inconsistent thickness, lack crisp embossed lot numbers, or are shipped loose without protective sealed pharmaceutical packaging.
06. Detailed Receptor Neurobiology & Dual-Mechanism Pain Pathway Pharmacology
Unlike classical pure μ-opioid receptor agonists, Tapentadol exhibits an innovative dual synergistic mechanism of action designed to attenuate both ascending nociceptive signals and augment descending inhibitory pain pathways within the central nervous system:
First, it binds directly to the μ-opioid receptor (MOR) located on presynaptic primary afferent neurons in the dorsal horn substantia gelatinosa and periaqueductal gray (PAG). Receptor coupling to inhibitory Gi/o proteins inhibits adenylate cyclase, reduces intracellular cyclic AMP, closes voltage-gated N-type calcium channels, and stimulates inward-rectifying potassium conductance. This presynaptic hyperpolarization directly suppresses the release of excitatory nociceptive neurotransmitters, specifically substance P, glutamate, and calcitonin gene-related peptide (CGRP).
Second, Tapentadol produces potent monoamine reuptake inhibition. By blocking the norepinephrine transporter (NET), it substantially increases synaptic concentrations of norepinephrine in descending bulbospinal inhibitory tracts. Synaptic norepinephrine stimulates post-junctional α2-adrenergic receptors on secondary spinal projection neurons, evoking hyperpolarization that blocks dorsal horn nociceptive transmission.
| PHARMACOLOGICAL TARGET | NEUROANATOMICAL SITE | MOLECULAR MECHANISM | CLINICAL ANALGESIC MANIFESTATION |
|---|---|---|---|
| μ-Opioid Receptor (MOR) | Dorsal horn substantia gelatinosa, periaqueductal gray | Gi/o-protein coupling, calcium channel blockade | Immediate suppression of acute nociceptive pain and visceral trauma |
| Norepinephrine Transporter (NET) | Descending bulbospinal tract, locus coeruleus projections | Neuronal reuptake inhibition, elevated synaptic NE | Potent relief of chronic neuropathic, radicular, and central sensitization pain |
| α2-Adrenoceptor Agonism | Dorsal horn interneurons and second-order projection neurons | Spinal inhibitory hyperpolarization | Synergistic opioid-sparing effect, enabling lower therapeutic doses |
| Mu-Opioid Spare Fraction | Intrinsic spinal antinociceptive circuit | Balanced dual-action synergy | Markedly lower GI adverse burden compared to classical opioids |
Because the noradrenergic component contributes up to 50% of the total analgesic efficacy, Tapentadol requires significantly less μ-opioid receptor occupancy than traditional opioids to achieve equivalent analgesia. This molecular architecture results in a markedly superior gastrointestinal safety profile, characterized by reduced incidence of severe constipation, respiratory depression, and rapid tolerance development.
07. Hepatic Clearance, Renal Impairment & Beers Criteria Safety
Safe clinical application of Tapentadol demands precise evaluation of metabolic pathways and organ clearance kinetics. Unlike many conventional medications, elimination characteristics differ significantly across patient populations:
| CLINICAL SUBGROUP | PHARMACOKINETIC KINETICS | DOSING MODIFICATION PROTOCOL | SAFETY / MONITORING DIRECTIVE |
|---|---|---|---|
| Mild Hepatic Impairment (Child-Pugh A) | Slight clearance reduction, normal volume of distribution | Standard adult starting dose; titrate with conservative intervals | Monitor for augmented somnolence or dizziness |
| Moderate Hepatic Impairment (Child-Pugh B) | Systemic exposure (AUC) increased 2- to 3-fold | Extend dosing interval to every 8 to 12 hours; 50mg initial cap | Strict clinical observation; monitor transaminases |
| Severe Hepatic Impairment (Child-Pugh C) | Marked metabolic shunting, unpredictable elimination | Contraindicated; alternative analgesic pathways mandated | Risk of profound CNS sedation and drug accumulation |
| Renal Impairment (CrCl < 30 mL/min) | Impaired clearance of polar glucuronide or active metabolites | Extend dosing interval; avoid exceeding minimum therapeutic threshold | Monitor creatinine clearance and signs of cognitive blunting |
| Geriatric Patients (≥ 65 Years) | Decreased glomerular filtration, heightened CNS sensitivity | Initiate at the lowest manufactured strength (50mg / dose) | Fall precautions, orthostatic monitoring, Beers Criteria review |
Under the American Geriatrics Society (AGS) Beers Criteria®, central-acting analgesics require judicious prescriber oversight in older adults due to age-related declines in neuromuscular coordination, cognitive reserve, and renal clearance. Where indicated, starting doses must be conservative with scheduled safety checks.
08. Comprehensive Patient Clinical Safety & Dispensing Checklist
Before initiating therapy or taking each scheduled dose of Tapentadol, patients, caregivers, and clinical teams must review this standardized clinical verification checklist to prevent adverse drug events and dangerous drug-drug interactions:
PATIENT PRE-ADMINISTRATION SAFETY CRITERIA
- Alcohol Abstinence Verification: Strict zero-tolerance for ethanol ingestion. Combining alcohol with central-acting analgesics causes synergistic CNS and respiratory depression, which can be fatal.
- Concurrent CNS Depressant & Benzodiazepine Screen: Ensure no simultaneous dosing with sedatives, tranquilizers, or sleep aids unless specifically managed under multi-specialist clinical oversight.
- Serotonergic Agent Co-Prescription Assessment: Confirm patient is not concurrently taking MAO inhibitors (contraindicated within 14 days), high-dose SSRIs, SNRIs, or triptans to prevent the development of life-threatening Serotonin Syndrome.
- Respiratory & Bronchial Function Evaluation: Withhold administration if patient exhibits acute severe asthma, hypercapnia, or respiratory compromise in unmonitored settings.
- Seizure History & Threshold Assessment: Screen for past epileptic episodes or concomitant medications that lower seizure threshold (especially relevant for monoamine-active analgesics).
- Locked Storage & Secure Disposal: Maintain medication in its original child-resistant blister packaging within a locked lockbox at controlled room temperature (20°C to 25°C / 68°F to 77°F). Never store in bathroom medicine cabinets where humidity fluctuates.
09. Verified Pharmaceutical Formulations & Prescribing Profiles

Aspadol 100mg (Tapentadol)
Dual-action centrally acting analgesic combining μ-opioid receptor agonism with norepinephrine reuptake inhibition for severe acute and neuropathic pain management.
10. Frequently Asked Questions
What color should authentic Aspadol 100mg tablets be?
Aspadol 100mg tablets feature a smooth, uniform pale-orange or peach-colored film coating with crisp edges and a clean central score line.
How can I tell if my tapentadol blister packaging is legitimate?
Legitimate blister packs feature crisp metallic backing foil with clear typography, embossed batch lot numbers, and matching expiration dates. The foil should resist peeling and require deliberate thumb pressure to punch through.
Can tapentadol tablets be cut in half along the score line?
Immediate-release 100mg tablets with functional score lines can be cleanly halved using a pharmacy pill cutter to administer a 50mg dose under physician direction. Extended-release tablets must never be cut.
Why are authentic tapentadol tablets blister packed rather than loose in bottles?
Blister packaging provides moisture protection, child resistance, unit-dose tracking, and verifiable tamper evidence to prevent counterfeit substitution during transport.
What should I do if my tablets arrive loose or damaged?
Never consume unsealed or loose tablets. Immediately contact the dispensing clinical pharmacy team with high-resolution photos of the packaging and lot numbers for safety evaluation.
11. Clinical References & Regulatory Sources
- United States Pharmacopeia (USP). Tapentadol Tablets Monograph. Source Database.
- DEA Drug Enforcement Administration. Counterfeit Prescription Pills and Synthetic Opioid Adulteration. Source Database.
- FDA CDER. Pill Identification and Regulatory Drug Quality Guidance. Source Database.
Consult a Clinical Pharmacy Specialist
Have questions regarding Tapentadol dosing intervals, CYP enzyme interactions, or physician-guided discontinuation protocols? Connect with our licensed clinical pharmacy team for patient safety guidance.
Related Patient Services & Verified Care
Every prescription order is verified by a licensed pharmacist in strict adherence to FDA BeSafeRx protocols.