

How to Legally Fill an Oxycodone Prescription Online: DEA Schedule II Rules, EPCS Verification, and Sourcing Standards

How to Legally Fill an Oxycodone Prescription Online: DEA Schedule II Rules, EPCS Verification, and Sourcing Standards
A regulatory and patient safety guide to legally obtaining prescription oxycodone through accredited digital pharmacies under federal Schedule II mandates.
PATIENT DISPENSING STANDARDS
EXECUTIVE CLINICAL SUMMARY
Oxycodone Hydrochloride (IR and ER) is classified as a Schedule II controlled substance under the United States Controlled Substances Act (CSA) and is subject to the most rigorous dispensing regulations in federal medicine. Because illicit internet black markets and fraudulent websites heavily target pain patients with counterfeit, fentanyl-pressed pills, patients must understand federal dispensing requirements. Under federal law, no refills are ever permitted on Schedule II prescriptions, and medications can only be dispensed via DEA-certified Electronic Prescriptions for Controlled Substances (EPCS) through licensed, VIPPS/NABP-accredited digital pharmacies.
01. Federal Schedule II controlled substance framework: Prescribing mandates
Under federal controlled substances statutes, oxycodone dispensing is governed by strict legal boundaries:
- Zero Refills Permitted: Federal law strictly prohibits automatic refills or call-in phone refills for Schedule II drugs. Every single dispensing event requires a brand-new prescription issued by a DEA-registered prescriber.
- Mandatory EPCS Technology: Prescriptions transmitted electronically must utilize DEA-certified Electronic Prescriptions for Controlled Substances (EPCS) software featuring two-factor practitioner authentication.
- Prohibition of Verbal Phone Orders: Pharmacists cannot accept verbal phone prescriptions except in verified immediate inpatient emergencies, and must receive a written or EPCS script within 7 days.
02. Checklist for identifying accredited digital pharmacies
Patients must verify critical dispensary credentials before transferring prescriptions or providing payment information.
| REGULATORY BENCHMARK | LICENSED ACCREDITED DIGITAL PHARMACY | ROGUE / ILLICIT ONLINE VENDOR | PATIENT HEALTH & LEGAL HAZARD |
|---|---|---|---|
| Prescription Verification | Requires DEA-authenticated EPCS script | Claims “No Prescription Needed” or “No Rx Required” | Severe federal criminal prosecution; fatal counterfeit pills |
| Accreditation Seals | Verified NABP / .Pharmacy domain certification | Fake logo images; untraceable offshore web domains | Credit card fraud; identity theft; personal data leaks |
| State Pharmacy Board Licensing | Holds active permits in patient’s resident state | Unlicensed or operating from unregulated foreign hubs | Medication seized by US Customs & Border Protection (CBP) |
| Pharmacist Consultation | Mandatory toll-free access to licensed pharmacists | Automated bots or non-clinical sales representatives | Zero review of deadly acetaminophen or opioid interactions |
| Supply Chain Integrity | Sourced directly from FDA-registered US distributors | Shipped loose from clandestine overseas pill presses | Lethal synthetic fentanyl or industrial toxic chemical poisoning |
03. The lethal danger of “No-Rx” online oxycodone vendors
Any website, social media profile, or messaging group claiming to sell oxycodone 30mg (M30) “without a prescription” is operating an illegal criminal enterprise. Forensic chemical testing by the DEA reveals that over 70% of pills purchased from unregulated internet sources contain lethal doses of illicit fentanyl or synthetic nitazenes. A single counterfeit pill can cause immediate respiratory arrest and death. Legitimate pharmacies never sell Schedule II opioids without a doctor’s verified prescription.
04. Tamper-evident packaging and delivery standards
When receiving genuine prescription oxycodone from a certified digital dispensary, patients must verify physical security standards:
- Discreet Opaque Packaging: Medication must arrive in unmarked, opaque packaging with zero exterior markings indicating opioid or pharmaceutical contents.
- Child-Resistant Amber Vials: Tablets must be sealed inside child-resistant containers with unbroken safety seals, featuring a complete prescription label displaying patient name, doctor, NDC code, and federal caution warning.
- Adult Signature Required: Federal delivery protocols mandate that controlled substances require an adult signature upon delivery to prevent theft or interception by minors.
05. Telehealth consultations: Modern electronic prescribing pathways
Patients recovering from recent surgeries, managing acute traumatic injuries, or dealing with severe oncology pain can legally consult with licensed physicians through accredited, HIPAA-compliant telehealth platforms. If clinically warranted after a thorough medical and Prescription Drug Monitoring Program (PDMP) review, the clinician transmits a secure EPCS prescription directly to the patient’s accredited digital pharmacy for rapid home dispensing.
06. Detailed Receptor Neurobiology, CYP2D6 Hydromorphone Bioactivation & APAP Synergy
At the molecular and clinical level, Oxycodone combines two distinct, synergistic analgesic compounds designed to attack nociceptive signaling through dual central and peripheral mechanisms:
1. Hydrocodone Component: Hydrocodone is a semi-synthetic phenanthrene opioid agonist that binds selectively to the μ-opioid receptor (MOR) on primary afferent neurons in the dorsal horn substantia gelatinosa and brainstem periaqueductal gray (PAG). Receptor coupling to inhibitory Gi/o proteins inhibits adenylyl cyclase, closes N-type voltage-gated calcium channels, and stimulates inward-rectifying potassium channels. This hyperpolarizes neuronal membranes, dramatically inhibiting presynaptic release of substance P, glutamate, and neurokinins.
Furthermore, hydrocodone undergoes critical hepatic O-demethylation catalyzed by cytochrome P450 2D6 (CYP2D6) into hydromorphone. Hydromorphone exhibits a 6- to 10-fold higher binding affinity for μ-opioid receptors than parent hydrocodone, contributing significantly to clinical analgesia. Patients who are CYP2D6 poor metabolizers experience diminished pain relief, whereas ultra-rapid metabolizers risk exaggerated sedation and respiratory depression.
2. Acetaminophen (APAP) Component: Acetaminophen produces analgesia primarily through central inhibition of cyclooxygenase (COX-1, COX-2, and putative central COX-3/peroxidase variants) and modulation of endogenous cannabinoid and descending serotonergic inhibitory pathways. Unlike NSAIDs, APAP lacks peripheral anti-inflammatory effects and does not cause gastric ulceration or platelet inhibition.
| PHARMACOLOGICAL AGENT | PRIMARY MOLECULAR TARGET | HEPATIC METABOLIC ENZYME | CLINICAL ANALGESIC ROLE | CRITICAL CLINICAL HAZARD |
|---|---|---|---|---|
| Hydrocodone | μ-Opioid Receptor (MOR) Agonism | CYP2D6 (to Hydromorphone) & CYP3A4 (to Norhydrocodone) | Blocks ascending nociceptive pain signaling in spinal cord | Respiratory depression, physical dependence, constipation |
| Acetaminophen (APAP) | Central COX / Peroxidase Site Inhibition | Glucuronidation (55%), Sulfation (30%), CYP2E1 (to NAPQI) | Synergistic pain threshold elevation; opioid-sparing effect | Hepatotoxicity / Centrilobular necrosis at >4,000mg/day |
| Hydromorphone (Metabolite) | High-Affinity μ-Opioid Agonist (Ki ~0.37 nM) | Phase II Glucuronidation via UGT2B7 | Potent amplification of central analgesic efficacy | Toxicity in CYP2D6 ultra-rapid metabolizers |
| NAPQI (Reactive Metabolite) | Hepatocyte macromolecules | Detoxified by intracellular glutathione (GSH) | None (Toxic intermediate) | Glutathione depletion leads to irreversible liver failure |
The combination of hydrocodone with acetaminophen creates potent therapeutic synergy, enabling lower doses of the opioid component while maximizing relief for moderate to severe acute musculoskeletal and post-surgical pain.
07. Hepatic Clearance, Renal Impairment & Beers Criteria Safety
Pharmacokinetic clearance of Oxycodone involves dual metabolic pathways for both hydrocodone and acetaminophen, requiring strict clinician oversight across specific organ impairment subgroups:
| PATIENT POPULATION | PHARMACOKINETIC KINETICS | DOSING MODIFICATION DIRECTIVE | CRITICAL CLINICAL MANDATE |
|---|---|---|---|
| Hepatic Impairment (Mild-Moderate) | Impaired APAP glucuronidation and reduced hydrocodone clearance | Cap APAP ≤2,000mg / 24 hours; extend dosing intervals to Q8H-Q12H | Monitor transaminases; avoid in acute hepatitis or liver decompensation |
| Severe Hepatic Cirrhosis (Child-Pugh C) | Glutathione depletion; severe hydrocodone metabolic shunting | CONTRAINDICATED: Extreme hepatotoxicity & encephalopathy risk | NAPQI accumulation precipitates fatal hepatic centrilobular necrosis |
| CYP2D6 Poor Metabolizers (~7% Caucasians) | Minimal conversion of hydrocodone to active hydromorphone | Evaluate alternative analgesics; do not dangerously escalate dose | Escalating doses causes toxic hydrocodone/APAP buildup without pain relief |
| CYP2D6 Ultra-Rapid Metabolizers | Rapid, massive bioactivation into hydromorphone | Initiate at 50% standard starting dose; monitor breathing | High risk of sudden, life-threatening respiratory depression |
| Renal Impairment (CrCl < 30 mL/min) | Prolonged hydrocodone elimination half-life; APAP metabolite retention | Increase dosing intervals to every 8 to 12 hours | Monitor for severe cognitive blunting and respiratory depression |
| Geriatric Patients (≥ 65 Years) | Decreased hepatic mass, diminished renal clearance, CNS sensitivity | Start at lowest manufactured dose (e.g. 5/325mg); Beers Criteria oversight | Proactive bowel management mandatory to prevent severe fecal impaction |
Absolute Daily Acetaminophen (APAP) Ceiling: Under FDA regulations, the total cumulative daily dose of acetaminophen from all sources combined (including OTC cough/cold elixirs, sinus remedies, and headache pills) must never exceed 4,000mg per 24 hours. For chronic or elderly patients, clinicians recommend a safer conservative threshold of 3,000mg daily (or ≤2,000mg in chronic alcohol consumers) to protect hepatic glutathione reserves.
08. Comprehensive Patient Clinical Safety & Dispensing Checklist
Before initiating therapy or taking each scheduled dose of Oxycodone, patients, caregivers, and clinical teams must review this standardized clinical verification checklist to prevent life-threatening adverse drug events and fatal toxicities:
PATIENT PRE-ADMINISTRATION SAFETY CRITERIA
- Total Acetaminophen (APAP) Audit: Verify that the patient is not taking ANY other products containing acetaminophen (e.g., Tylenol, DayQuil, NyQuil, Excedrin, Percocet). Total APAP from all sources must never exceed 4,000mg/day (clinically target ≤3,000mg/day).
- Absolute Alcohol Prohibition: Strict zero-tolerance for alcohol. Ethanol massively accelerates liver glutathione depletion (triggering acute liver failure from APAP) while paralyzing brainstem respiratory drive alongside hydrocodone.
- Concurrent Benzodiazepine & Sedative Screen: Check for co-prescribed anti-anxiety drugs (alprazolam, diazepam, lorazepam) or sleep aids. The FDA Boxed Warning strictly advises against co-prescribing without active emergency naloxone on site.
- Emergency Naloxone (Narcan) Access: Ensure household members or caregivers know the location of emergency naloxone nasal spray and how to administer it in case of accidental overdose or respiratory collapse.
- Proactive Bowel Regimen Initiation: Opioids inevitably cause opioid-induced constipation (OIC) by paralyzing gastrointestinal motility. Daily fluid intake, dietary fiber, and scheduled osmotic or stimulant laxatives (senna, PEG 3350) should begin with the very first dose.
- Locked Storage & Disposal Safeguards: Store securely in a locked lockbox out of sight and reach of children, visitors, and pets. Accidental single-tablet ingestion of 10mg hydrocodone can cause fatal respiratory arrest in a toddler.
09. Verified Pharmaceutical Formulations & Prescribing Profiles
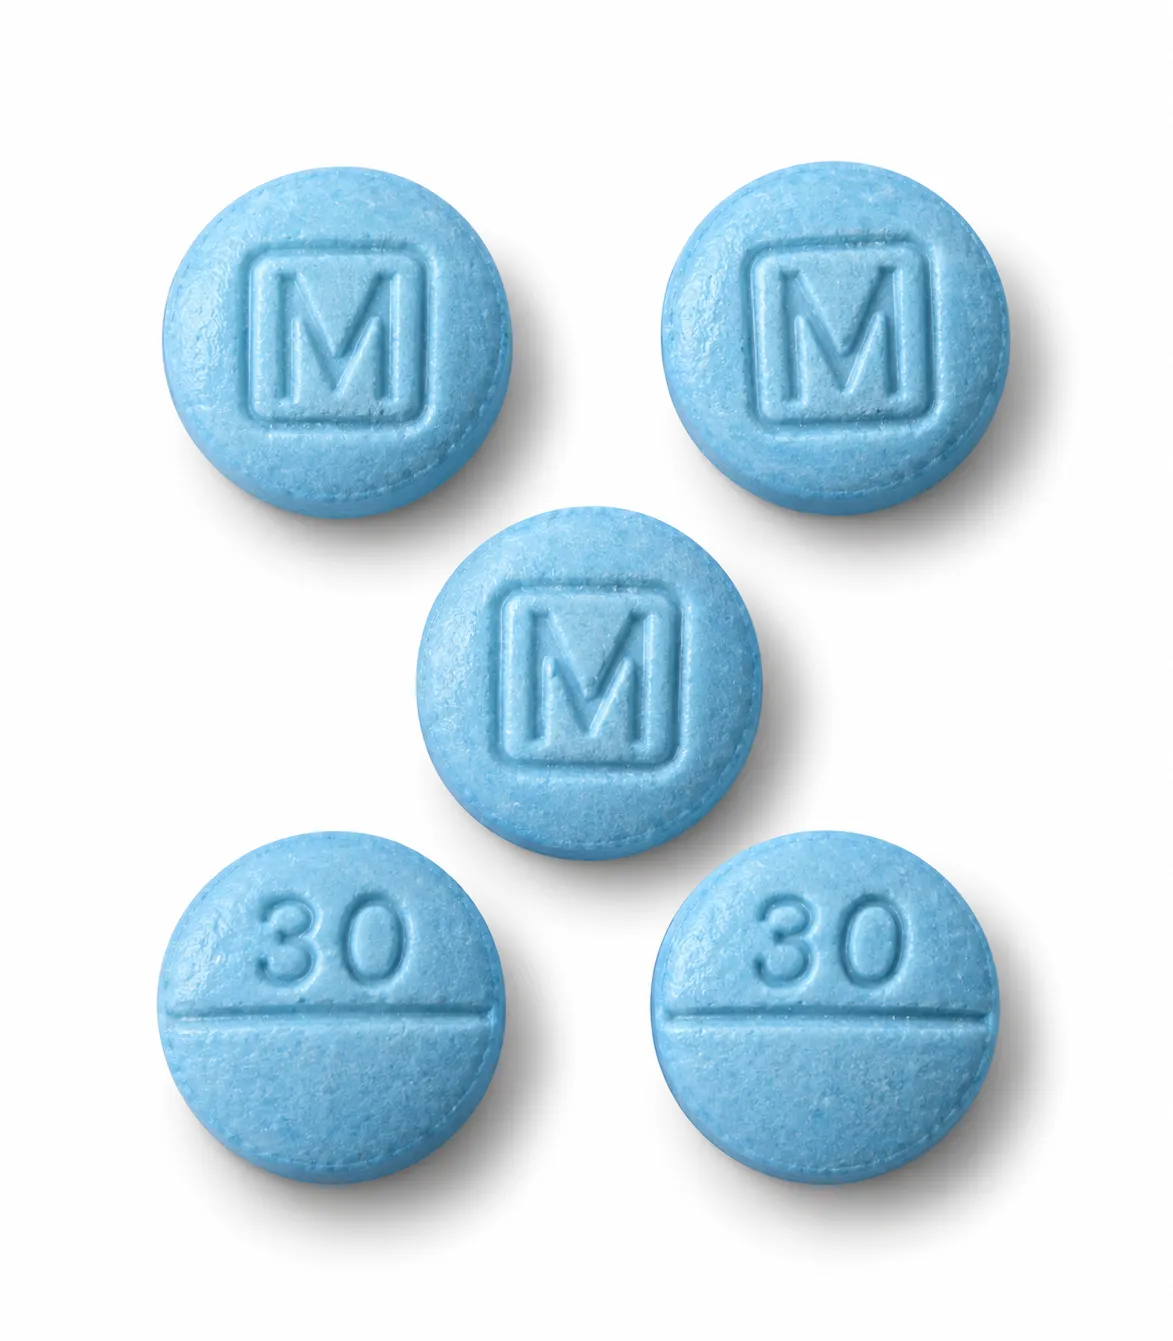
Oxy M30 (Oxycodone IR 30mg)
Immediate-release 30mg oral tablets for severe acute post-surgical and breakthrough cancer pain.

Percocet E712 (Oxycodone / APAP 10/325mg)
Dual-action combination analgesic for moderate to severe acute musculoskeletal trauma and surgical recovery.

Oxy 80mg Green (Oxycodone ER)
Continuous 12-hour extended-release formulation indicated exclusively for opioid-tolerant chronic cancer pain.
10. Frequently Asked Questions
Can you legally buy oxycodone online without a doctor’s prescription?
No. Oxycodone is a Schedule II controlled substance. Any website claiming to sell it without a prescription is illegal and selling counterfeit pills that frequently contain deadly fentanyl.
Can my doctor call in an oxycodone refill over the phone to the pharmacy?
No. Because oxycodone is a Schedule II drug, federal law does not allow automatic refills or standard phone-in prescriptions. A brand-new electronic prescription (EPCS) is required for every single bottle.
How can I verify that an online pharmacy is legitimate?
Check that the pharmacy is accredited by the National Association of Boards of Pharmacy (NABP), requires a doctor’s prescription, has a licensed US pharmacist available for questions, and holds a state pharmacy license.
Does an oxycodone delivery require a signature at the door?
Yes. Accredited pharmacies use secure, tracked shipping methods that require an adult signature upon delivery to ensure controlled medications are received safely.
11. Clinical References & Regulatory Sources
- United States Drug Enforcement Administration (DEA). Controlled Substances Act Regulations: Schedule II Oxycodone. Source Database.
- National Association of Boards of Pharmacy (NABP). Digital Pharmacy Accreditation and Consumer Safety Standards. Source Database.
- FDA CDER. Electronic Prescriptions for Controlled Substances (EPCS) and Safe Online Pharmacy Verification. Source Database.
Consult a Clinical Pharmacy Specialist
Have questions regarding Oxycodone dosing intervals, CYP enzyme interactions, or physician-guided discontinuation protocols? Connect with our licensed clinical pharmacy team for patient safety guidance.
Related Patient Services & Verified Care
Every prescription order is verified by a licensed pharmacist in strict adherence to FDA BeSafeRx protocols.