
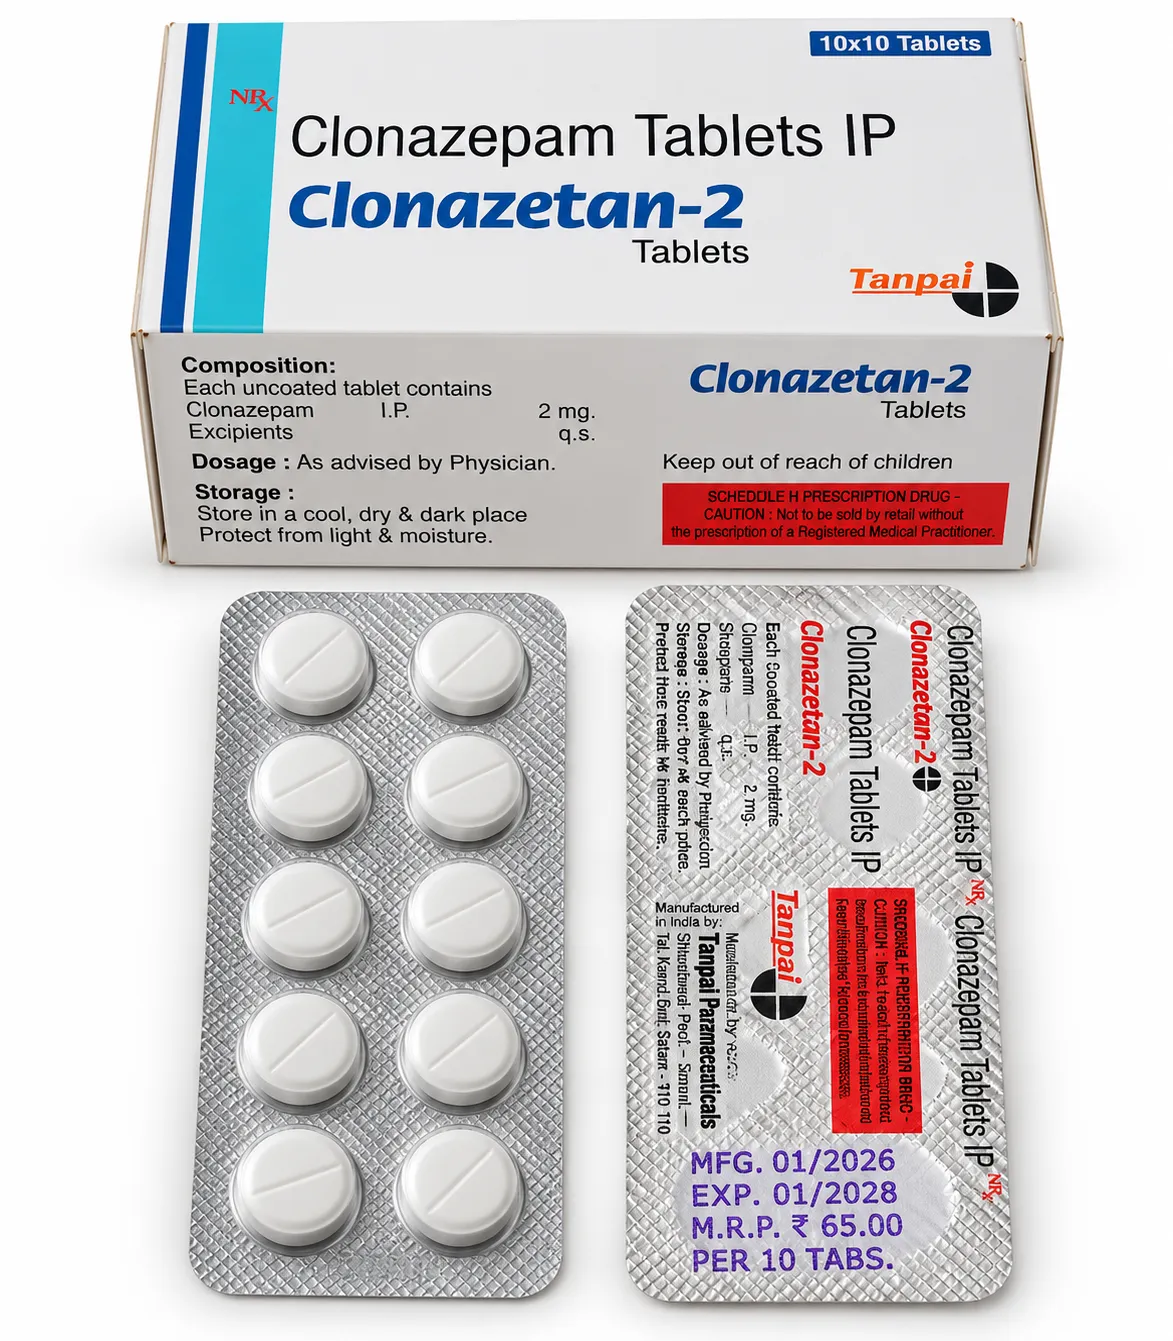
Clonazepam Tapering Schedule: The Ashton Method, Micro-Tapering Protocols, and Safe Deprescribing Guidelines

Clonazepam Tapering Schedule: The Ashton Method, Micro-Tapering Protocols, and Safe Deprescribing Guidelines
A comprehensive clinical tapering guide for discontinuing clonazepam safely, avoiding protracted withdrawal syndrome and rebound panic.
CLINICAL DEPRESCRIBING PROTOCOL
EXECUTIVE CLINICAL SUMMARY
Discontinuing clonazepam (Klonopin®) after chronic daily administration requires meticulous clinical planning and gradual deprescribing. Because clonazepam is an exceptionally potent benzodiazepine (0.5mg clonazepam is clinically equivalent to approximately 10mg of diazepam), cutting doses too rapidly triggers severe physiological rebound, autonomic instability, muscle fasciculations, sensory hyperacusis, and life-threatening withdrawal seizures. The gold-standard clinical framework for deprescribing is the Ashton Method—which either cross-tapers the patient onto an equivalent dose of the ultra-long-acting agent diazepam (Valium®) or utilizes precision clonazepam micro-tapering (5% to 10% reductions every 2 to 4 weeks) to allow GABA-A neuroreceptors to safely recalibrate.
01. The neurobiology of benzodiazepine withdrawal: GABA down-regulation and NMDA excess
Chronic daily clonazepam administration leads to profound neurochemical adaptations:
- GABA-A Subunit Internalization: Neurons internalize and down-regulate inhibitory GABA-A receptor complexes, reducing endogenous inhibitory tone.
- Glutamatergic NMDA Upregulation: In compensatory response, the brain up-regulates excitatory N-methyl-D-aspartate (NMDA) and AMPA glutamate receptors to maintain baseline consciousness.
- The Excitotoxic Storm: When clonazepam is removed abruptly, inhibitory braking is eliminated while excitatory glutamate cascades fire unchecked, inducing panic, tremors, severe insomnia, hyperthermia, and convulsions.
02. The Ashton Protocol: Stepwise cross-over from clonazepam to diazepam
Professor C. Heather Ashton’s protocol substitutes clonazepam with equivalent doses of diazepam, providing smooth 24-hour plasma concentrations via diazepam’s active metabolites and allowing small, milligram-level dose reductions.
| TAPER STAGE | MORNING DOSE | MID-DAY DOSE | NIGHTTIME DOSE | TOTAL DIAZEPAM EQUIVALENT | CLINICAL ACTION |
|---|---|---|---|---|---|
| Baseline | Clonazepam 0.5mg | – | Clonazepam 0.5mg | 20mg Diazepam Eq. | Establish stable baseline daily dosing (1.0mg total) |
| Stage 1 (Weeks 1-2) | Clonazepam 0.5mg | – | Diazepam 10mg | 20mg Diazepam Eq. | Substitute evening clonazepam with diazepam 10mg |
| Stage 2 (Weeks 3-4) | Diazepam 10mg | – | Diazepam 10mg | 20mg Diazepam Eq. | Substitute morning clonazepam; 100% on diazepam |
| Stage 3 (Weeks 5-6) | Diazepam 8mg | – | Diazepam 10mg | 18mg Diazepam | Begin 2mg bi-weekly diazepam reductions |
| Stage 4 (Weeks 7-14) | Stepwise -2mg every 2 weeks across morning/night | – | Maintain evening dose | 8mg to 16mg Diazepam | Gradual de-escalation; monitor autonomic stability |
| Stage 5 (Weeks 15-22) | Diazepam 1mg – 2mg | – | Diazepam 2mg – 4mg | 3mg to 6mg Diazepam | Micro-titration; utilize liquid diazepam if needed |
| Stage 6 (Weeks 23+) | 0mg | – | 0mg | 0mg | Full cessation; evaluate non-pharmacological support |
03. Direct clonazepam micro-tapering (When diazepam cross-over is not tolerated)
Some patients cannot tolerate diazepam due to sedation, active metabolite accumulation, or hepatic impairment. In these cases, a direct clonazepam micro-taper is conducted using commercially prepared oral liquid solutions (0.1 mg/mL) or compounded micro-tablets. Reductions are restricted to no more than 5% to 10% of the current dose every 14 to 28 days, allowing the patient’s clinical symptoms to dictate the pace of reduction.
04. Managing somatic and psychological withdrawal symptoms
A patient undergoing a gradual taper should expect mild, transient withdrawal phenomena that are safe and manageable:
- Sensory Hyperacusis: Heightened sensitivity to light, sound, and skin touch as sensory filtering networks recalibrate.
- Muscle Tension & Twitches: Benign fasciculations in the legs, arms, and eyelids.
- REM Sleep Rebound: Intense, vivid dreams during the first few days following a dose cut.
- Adjunctive Medications: Clinicians may prescribe non-GABA medications—such as propranolol (to block physical adrenaline spikes and tachycardia) or gabapentin—to smooth the deprescribing process.
05. Protracted Benzodiazepine Withdrawal Syndrome (PAWS) prevention
Rapid detox or cold-turkey cessation is the single greatest risk factor for developing Protracted Benzodiazepine Withdrawal Syndrome (PAWS)—a debilitating condition characterized by persistent waves of anxiety, tinnitus, gastrointestinal distress, and depersonalization lasting for months or years. A slow, patient-centered taper is the only validated method to prevent PAWS and ensure permanent medication independence.
06. Detailed Receptor Neurobiology & GABA-A Subunit Pharmacology
At the molecular level, Clonazepam functions as a positive allosteric modulator of the gamma-aminobutyric acid type A (GABA-A) receptor complex, the primary inhibitory neurotransmitter system in the mammalian central nervous system. The pentameric GABA-A receptor spans the neuronal cell membrane, typically comprising two alpha (α), two beta (β), and one gamma (γ) subunit arranged around a central chloride ion pore.
Clonazepam binds stereospecifically to the high-affinity allosteric pocket located at the interface of the α and γ2 subunits. Crucially, binding does not directly open the chloride channel in the absence of GABA; rather, it induces a conformational change that increases the affinity of the receptor for endogenous GABA, significantly augmenting the frequency of chloride channel opening bursts.
| GABA-A SUBUNIT ISOFORM | ANATOMICAL DISTRIBUTION | PRIMARY CLINICAL EFFECT | THERAPEUTIC MANIFESTATION |
|---|---|---|---|
| α1 Subunit | Cerebral cortex, cerebellum, thalamus | Sedation, anterograde amnesia, ataxia | Hypnotic effect, sleep latency reduction |
| α2 Subunit | Limbic system, amygdala, striatum | Anxiolysis, emotional tranquility | Suppression of acute panic, fear extinction |
| α3 Subunit | Spinal cord motor neurons, reticular formation | Muscle relaxation, sensorimotor gating | Spasticity reduction, central tone relief |
| α5 Subunit | Hippocampus, temporal lobe circuits | Temporal memory encoding, cognition | Mild cognitive slowing, tolerance onset |
The resulting influx of extracellular chloride ions into the neuronal cytoplasm hyperpolarizes the postsynaptic resting membrane potential from approximately -70 mV to -85 mV. This electrical hyperpolarization elevates the threshold required to fire action potentials, fundamentally quieting hyperactive neural circuits within the amygdalar-cortical anxiety axis.
07. Hepatic Clearance, Renal Impairment & Beers Criteria Safety
Because Clonazepam undergoes extensive oxidative hepatic biotransformation and subsequent phase II conjugation before undergoing renal excretion, therapeutic drug monitoring and dose titrations must be carefully tailored in patients with compromised organ clearance:
| CLINICAL POPULATION | PHARMACOKINETIC ALTERATION | RECOMMENDED DOSING STRATEGY | PRIMARY RISK FACTOR |
|---|---|---|---|
| Hepatic Insufficiency (Child-Pugh A/B) | Decreased clearance, prolonged elimination half-life | Initiate at 50% standard adult dose; monitor hepatic enzymes | Severe medication accumulation, excessive daytime sedation |
| Severe Hepatic Cirrhosis (Child-Pugh C) | Profound metabolic impairment, shunting of portal blood | Contraindicated or strict specialist supervision only | Hepatic encephalopathy precipitation |
| Renal Impairment (CrCl < 30 mL/min) | Impaired clearance of active polar metabolites | Titrate slowly with prolonged inter-dose intervals | Metabolite accumulation, lingering psychomotor slowing |
| Geriatric Patients (≥ 65 Years) | Reduced volume of distribution, lower plasma albumin binding | Maximum initial dose: 50% of adult dose (Beers Criteria) | Ataxia, nocturnal confusion, hip fractures, motor vehicle accidents |
Under the American Geriatrics Society (AGS) Beers Criteria®, central nervous system depressants in this therapeutic class are designated as Potentially Inappropriate Medications (PIMs) in older adults due to heightened pharmacodynamic sensitivity, slower metabolic biotransformation, and markedly increased risk of falls, motor vehicle trauma, and acute delirium. Where clinical indications necessitate treatment, medical guidelines mandate starting at the lowest effective dose for the briefest possible clinical duration.
08. Comprehensive Patient Clinical Safety & Dispensing Checklist
Before initiating therapy or taking each scheduled dose of Clonazepam, patients, caregivers, and healthcare providers must review this standardized clinical verification checklist to prevent adverse drug events and dangerous interactions:
PATIENT PRE-ADMINISTRATION SAFETY CRITERIA
- Alcohol Abstinence Verification: Confirm zero consumption of wine, beer, spirits, or ethanol-containing over-the-counter elixirs within the past 24 hours. Co-ingestion exponentially raises fatal respiratory depression risks.
- Concurrent Opioid Assessment: Ensure no simultaneous dosing with prescription opioids (oxycodone, hydrocodone, tramadol, codeine) unless specifically authorized under dual-prescribing protocols with an active naloxone rescue kit on hand.
- Respiratory Function Check: Withhold administration and seek immediate medical evaluation if experiencing acute respiratory distress, severe sleep apnea hypopnea, or COPD exacerbation.
- Motor Vehicle & Machinery Clearance: Confirm that no driving, hazardous equipment operation, or critical decision-making is scheduled for at least 8 to 12 hours post-dose.
- Safe Storage & Child Resistance: Verify that medication is stored in its original labeled container inside a locked medicine cabinet at controlled room temperature (20°C to 25°C / 68°F to 77°F), completely out of reach of children and pets.
09. Verified Pharmaceutical Formulations & Prescribing Profiles
Clonazepam 2mg (Klonopin Lineage)
High-potency, long-acting anticonvulsant and anxiolytic indicated for panic disorder, Lennox-Gastaut syndrome, and seizure prophylaxis.
10. Frequently Asked Questions
Why is it so hard to stop taking clonazepam 2mg?
Clonazepam is an extremely strong medication that alters brain receptor chemistry. Quitting too quickly causes an immediate rebound of severe anxiety, tremors, insomnia, and dangerous seizures.
What is the Ashton Method for tapering off clonazepam?
The Ashton Method is a doctor-supervised protocol that slowly replaces clonazepam with diazepam (Valium). Because diazepam lasts longer in the body, it allows for smooth, tiny reductions without painful withdrawal spikes.
How long should a clonazepam taper take?
A safe taper typically takes anywhere from 6 months to over a year, depending on your dose and how long you have been taking it. Going slow gives your brain time to heal.
Can I cut my 0.5mg clonazepam pills in half to quit on my own?
Cutting pills in half represents a 50% drop, which is far too large and dangerous. Reductions should never exceed 5% to 10% at a time under medical supervision.
11. Clinical References & Regulatory Sources
- Ashton CH. Benzodiazepines: How They Work and How to Withdraw (The Ashton Manual). Newcastle University. Source Database.
- The British Journal of Psychiatry. Slow tapering vs. abrupt withdrawal of long-term benzodiazepine users: Clinical outcomes. Source Database.
- JAMA Network Open. Management of benzodiazepine discontinuation and protracted withdrawal symptoms. Source Database.
Consult a Clinical Pharmacy Specialist
Have questions regarding Clonazepam dosing intervals, CYP enzyme interactions, or physician-guided discontinuation protocols? Connect with our licensed clinical pharmacy team for patient safety guidance.
Related Patient Services & Verified Care
Every prescription order is verified by a licensed pharmacist in strict adherence to FDA BeSafeRx protocols.