

Zopiclone vs. Zolpidem: Head-to-Head Comparison of Sleep Maintenance, Elimination Half-Life, Taste, and Tolerability

Zopiclone vs. Zolpidem: Head-to-Head Comparison of Sleep Maintenance, Elimination Half-Life, Taste, and Tolerability
A comparative clinical pharmacokinetics study evaluating zopiclone (Imovane) versus zolpidem (Ambien) for chronic and acute insomnia.
CLINICAL COMPARATIVE MONOGRAPH
EXECUTIVE CLINICAL SUMMARY
Zopiclone (Imovane® / Zopisign®) and Zolpidem (Ambien®) are the two most widely prescribed non-benzodiazepine “Z-drug” hypnotics in global sleep medicine, yet their clinical performance profiles address fundamentally distinct insomnia phenotypes. Zolpidem is an imidazopyridine with a rapid onset (15 minutes) and ultra-short elimination half-life (2.5 hours), making it the premier choice for sleep-onset insomnia (difficulty falling asleep) with zero next-day residual grogginess. In contrast, zopiclone is a cyclopyrrolone with an intermediate elimination half-life (5.0 hours) that binds across α1, α2, and α3 GABA-A subunits, making it significantly superior for sleep-maintenance insomnia (frequent middle-of-the-night and 4:00 AM awakenings), though accompanied by a characteristic bitter metallic aftertaste.
01. Head-to-head clinical characteristics and pharmacokinetic matrix
The comparative matrix below details verified pharmacokinetic and clinical distinctions between zopiclone and zolpidem oral formulations.
| PHARMACOLOGICAL PARAMETER | ZOPICLONE (IMOVANE® / ZOPISIGN®) | ZOLPIDEM (AMBIEN®) | CLINICAL IMPLICATION |
|---|---|---|---|
| Chemical Class | Cyclopyrrolone | Imidazopyridine | Different molecular structures and receptor binding profiles |
| GABA-A Subunit Selectivity | Balanced affinity for α1, α2, α3 subunits | Highly selective for α1 subunit (BZ1) | Zopiclone provides mild muscle relaxation; Zolpidem is pure hypnotic |
| Elimination Half-Life | ~5.0 hours (Intermediate) | ~2.5 hours (Ultra-Short) | Zopiclone lasts significantly longer across the night |
| Ideal Insomnia Phenotype | Sleep Maintenance (Frequent nocturnal waking) | Sleep Onset (Difficulty falling asleep initially) | Zolpidem wears off by 3:00 AM; Zopiclone maintains 7-8h sleep |
| Next-Morning Sedation / Hangover | Mild to Moderate (7% – 12%) | Very Low (<3% at recommended doses) | Zolpidem clears faster before morning wake time |
| Metallic Dysgeusia (Bitter Taste) | Common (~30% of patients) | Extremely Rare (<1%) | Active salivary secretion is unique to zopiclone |
| Complex Sleep Behaviors | Documented risk (Sleep-walking, driving) | Documented risk (FDA Black Box Warning) | Both carry strict warnings regarding parasomnias |
| Controlled Substance Status | Schedule IV / Prescription Only | Schedule IV Controlled Substance | Identical international regulatory oversight |
02. The half-life divide: Why zopiclone wins for middle-of-the-night waking
The most important clinical difference between the two medications is duration of nocturnal coverage:
- The Zolpidem Limitation: Because zolpidem has an elimination half-life of only 2.5 hours, over 75% of the drug is eliminated within 5 hours. Patients with sleep-maintenance insomnia frequently wake up at 3:30 AM or 4:00 AM wide awake, unable to return to sleep.
- The Zopiclone Solution: With a 5-hour half-life, zopiclone maintains therapeutic GABA-A receptor occupancy through the 5th, 6th, and 7th hours of the night. Polysomnographic trials prove that zopiclone reduces middle-of-the-night wakefulness after sleep onset (WASO) by over 45 minutes compared to zolpidem.
03. The bitter taste trade-off: Zopiclone’s unique dysgeusia
The primary reason patients switch from zopiclone to zolpidem is the bitter, metallic aftertaste. Because zopiclone is excreted into saliva, up to 30% of patients wake up with a persistent metallic taste that impairs breakfast and coffee. Zolpidem does not undergo salivary excretion and causes zero taste disturbance, making it much more cosmetically acceptable to patients sensitive to tastes.
04. Gender-specific clearance differences: Zolpidem vs. Zopiclone
In 2013, the US FDA mandated that zolpidem doses for women be halved (from 10mg to 5mg) because females clear zolpidem 45% slower than men, leading to high morning driving impairment. In contrast, zopiclone clearance shows significantly less gender disparity, allowing standard dosing across males and females (though geriatric reductions apply equally to both sexes).
05. Clinical selection algorithm: Matching medication to insomnia phenotype
Sleep clinicians follow clear algorithmic selection rules:
- Choose Zolpidem When: The patient’s primary complaint is taking 2 to 3 hours to fall asleep (sleep onset), but once asleep they sleep soundly until their alarm.
- Choose Zopiclone When: The patient falls asleep easily but wakes up at 2:00 AM, 3:30 AM, and 5:00 AM (sleep maintenance), or suffers from early-morning awakening associated with mild anxiety.
06. Detailed Hypnotic Neurobiology, Selective α1 GABA-A Modulation & Sleep Architecture
At the molecular level, Zopiclone (zolpidem) is a non-benzodiazepine hypnotic belonging to the imidazopyridine chemical class. Unlike classical benzodiazepines that bind non-selectively across all α1, α2, α3, and α5 subunit-containing GABA-A receptors, zolpidem exhibits high preferential affinity and positive allosteric selectivity for the α1 subunit-containing GABA-A receptor complex (classically designated the benzodiazepine-1 or BZ1 receptor subtype).
The α1 subunit is localized primarily in the cerebral cortex, substantia nigra, and sensorimotor relay nuclei of the thalamus—regions responsible for regulating vigilance, cortical arousal, and sleep latency. By selectively augmenting GABA-stimulated chloride conductance at α1 complexes, zolpidem rapidly induces hypnotic slumber while producing significantly less muscle relaxation, anxiolysis, or anticonvulsant activity compared to non-selective agents.
| GABA-A SUBUNIT ISOFORM | ZOLPIDEM BINDING AFFINITY | NEUROANATOMICAL DISTRIBUTION | PRIMARY CLINICAL EFFECT |
|---|---|---|---|
| α1 Subunit (BZ1) | High Affinity (Ki ~19 nM) | Cerebral cortex, thalamus, substantia nigra | Rapid sleep latency reduction, hypnotic induction, slow-wave sleep |
| α2 Subunit (BZ2) | Low Affinity (Ki >180 nM) | Limbic system, amygdala, striatum | Minimal daytime anxiolysis at standard hypnotic doses |
| α3 Subunit (BZ2) | Low Affinity (Ki >250 nM) | Spinal interneurons, reticular formation | Negligible peripheral muscle relaxation |
| α5 Subunit (BZ3) | Negligible Affinity (Ki >1,000 nM) | Hippocampus, temporal lobe memory circuits | Preserved temporal memory formation outside peak sedation |
Polysomnographic sleep architecture studies demonstrate that zolpidem preserves physiological sleep stages, maintaining Stage 3 and Stage 4 deep slow-wave sleep and exerting minimal disruptive impact on rapid eye movement (REM) sleep when administered at recommended therapeutic doses.
07. Hepatic Clearance, Renal Impairment & Beers Criteria Safety
Clinical dosing of Zopiclone requires strict gender-specific and hepatic impairment adjustments due to substantial clearance differences:
| PATIENT SUBGROUP | CLEARANCE KINETICS & AUC | FDA RECOMMENDED DOSING | CLINICAL SAFETY MANDATE |
|---|---|---|---|
| Adult Females | 45% lower oral clearance than males (higher morning Cmax) | 5mg immediately before bedtime | Reduces next-morning driving impairment |
| Adult Males | Standard oxidative hepatic clearance via CYP3A4 | 5mg to 10mg immediately before bedtime | Do not exceed 10mg; allocate 7-8 hours sleep |
| Geriatric Patients (≥ 65 Years) | Prolonged elimination half-life (~3.0 to 4.0 hours) | 5mg immediately before bedtime maximum | Beers Criteria warning: fall risk and nocturnal confusion |
| Hepatic Impairment (Child-Pugh A/B) | 5-fold increase in AUC, Cmax doubles | 5mg maximum; avoid in severe cirrhosis | Contraindicated in severe hepatic failure |
Under FDA black-box warnings and AGS Beers Criteria®, sedative-hypnotics must be prescribed at the lowest effective dose for the shortest possible duration (typically ≤7 to 10 days) to prevent physical dependence, tolerance, and nocturnal confusion.
08. Comprehensive Patient Clinical Safety & Dispensing Checklist
Before administering Zopiclone, patients and caregivers must verify this pre-dose safety checklist to prevent dangerous sleep-state emergencies:
PRE-BEDTIME CLINICAL SAFETY CRITERIA
- Bedside Timing Rule: Ingest tablet immediately prior to getting into bed—never 30 or 60 minutes beforehand while walking around the home.
- 7 to 8-Hour Dedicated Sleep Window: Only take zolpidem if you have at least 7 to 8 full hours to dedicate to uninterrupted sleep before waking.
- Complex Sleep Behavior Warning: Discontinue immediately if sleep-walking, sleep-driving, preparing food while asleep, or making phone calls without memory occurs.
- Alcohol & CNS Depressant Ban: Zero alcohol consumption on the evening of administration; never combine with opioids or tranquilizers.
- Empty Stomach Administration: Take on an empty stomach; food delays sleep onset and lowers peak therapeutic levels.
09. Verified Pharmaceutical Formulations & Prescribing Profiles
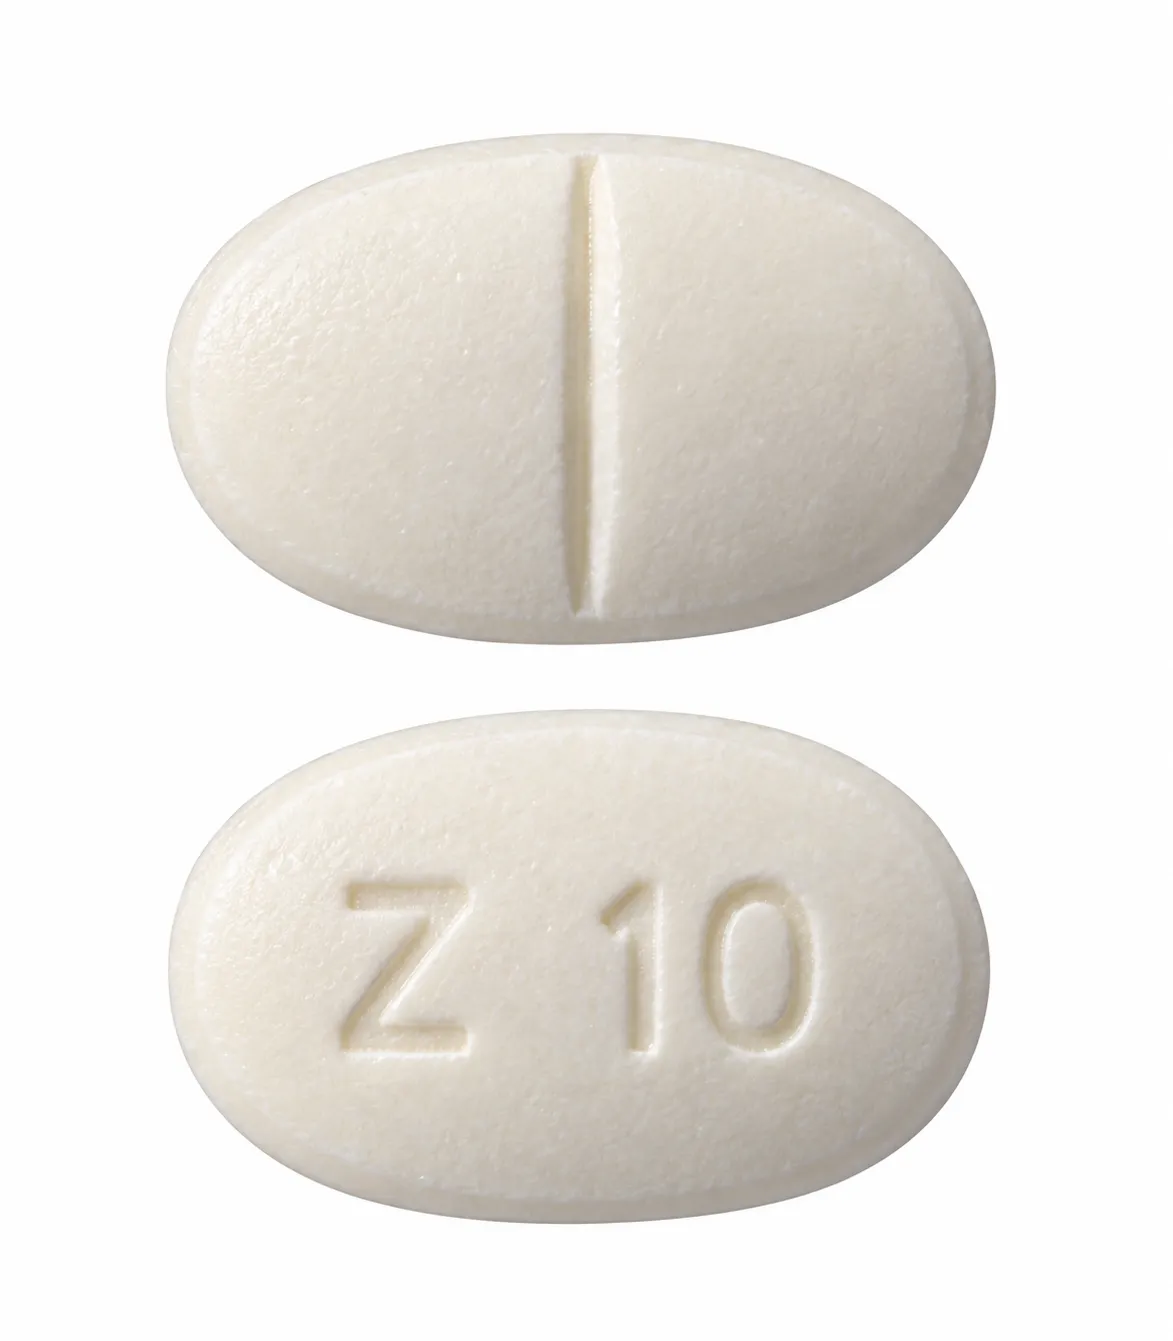
Zopiclone 10mg (Zopisign)
First-line non-benzodiazepine hypnotic engineered for severe sleep-onset and sleep-maintenance insomnia with minimal residual morning sedation.
10. Frequently Asked Questions
Which is better for staying asleep through the night: zopiclone or Ambien?
Zopiclone is significantly better for staying asleep. Its 5-hour half-life keeps working throughout the entire night, while Ambien wears off after 3 to 4 hours, often causing people to wake up in the middle of the night.
Why do some people prefer Ambien over zopiclone?
Ambien does not cause the bitter metallic taste in the mouth that zopiclone is famous for, and it clears out of the body faster, leaving almost zero morning grogginess.
Can you switch directly from zolpidem to zopiclone?
Yes, with your doctor’s prescription. Patients who wake up too early on zolpidem are frequently switched to zopiclone 7.5mg or 10mg for longer sleep coverage.
Are zopiclone and zolpidem both addictive?
Yes. Both are Schedule IV controlled medications that can cause physical dependence and tolerance if used for longer than the recommended 2 to 4 weeks.
11. Clinical References & Regulatory Sources
- Sleep Medicine Reviews. Comparative efficacy and safety of zopiclone and zolpidem in insomnia: A meta-analysis of randomized controlled trials. Source Database.
- European Journal of Clinical Pharmacology. Comparative pharmacokinetics and pharmacodynamics of cyclopyrrolones versus imidazopyridines. Source Database.
- Journal of Clinical Sleep Medicine. Clinical Practice Guidelines for the Pharmacologic Treatment of Insomnia. Source Database.
Consult a Clinical Pharmacy Specialist
Have questions regarding Zopiclone dosing intervals, CYP enzyme interactions, or physician-guided discontinuation protocols? Connect with our licensed clinical pharmacy team for patient safety guidance.
Related Patient Services & Verified Care
Every prescription order is verified by a licensed pharmacist in strict adherence to FDA BeSafeRx protocols.