

Hydrocodone Watson 853 vs. Mallinckrodt M367: Bioequivalence Data, Dissolution Rates, Inactive Fillers, and Patient Outcomes

Hydrocodone Watson 853 vs. Mallinckrodt M367: Bioequivalence Data, Dissolution Rates, Inactive Fillers, and Patient Outcomes
A comparative clinical pharmacokinetics review evaluating Watson 853 yellow tablets versus Mallinckrodt M367 white tablets for acute pain management.
CLINICAL COMPARATIVE PHARMACOKINETICS
EXECUTIVE CLINICAL SUMMARY
A widespread clinical debate among surgical patients and chronic pain sufferers is whether yellow Watson 853 tablets (Actavis/Teva) provide different pain relief or tolerability than white Mallinckrodt M367 tablets. Under FDA Orange Book criteria, both formulations are rated AB therapeutically equivalent, meaning their rate (Cmax) and extent (AUC) of systemic absorption fall within the statistical 90% confidence interval of 80.00% to 125.00% of the reference listed drug (Norco® 10/325mg). While the active active pharmaceutical ingredients (10mg hydrocodone bitartrate and 325mg acetaminophen) are chemically identical, differences in tablet core hardness, disintegrant excipients, and D&C Yellow No. 10 dye can cause subtle variations in gastric disintegration and patient preference.
01. Pharmacokinetic bioequivalence comparison: Watson vs. Mallinckrodt
The comparative matrix below details verified pharmacokinetic parameters demonstrated during FDA bioequivalence registration trials in healthy adult cohorts.
| PHARMACOKINETIC PARAMETER | WATSON 853 (TEVA/ACTAVIS) | MALLINCKRODT M367 | FDA ACCEPTANCE RANGE | CLINICAL INTERPRETATION |
|---|---|---|---|---|
| Active Hydrocodone Content | 10.0 mg (USP) | 10.0 mg (USP) | 95.0% – 105.0% Assay | Chemically identical μ-opioid receptor agonism |
| Active Acetaminophen Content | 325.0 mg (USP) | 325.0 mg (USP) | 95.0% – 105.0% Assay | Identical central COX-mediated pain threshold elevation |
| Peak Concentration (Cmax) | ~23.6 ng/mL (Reference) | ~24.1 ng/mL (102%) | 90% CI within 80.00% – 125.00% | Clinically indistinguishable peak plasma exposure |
| Total Systemic Exposure (AUC0-∞) | ~158 ng•h/mL | ~161 ng•h/mL (101.9%) | 90% CI within 80.00% – 125.00% | Identical total pain relief coverage over dosing cycle |
| Time to Peak (Tmax) | 1.3 hours | 1.4 hours | Comparable gastric breakdown | Both provide rapid analgesic onset within 20-30 minutes |
| Tablet Core Color & Shape | Pale Yellow Oblong Oval | Brilliant White Capsule | N/A (Proprietary cosmetic) | Cosmetic differentiation only |
02. Inactive excipient comparison: Binders, disintegrants, and dyes
The non-active structural excipients account for the physical differences between the two formulations:
- Watson 853: Formulated with microcrystalline cellulose, pregelatinized corn starch, croscarmellose sodium, magnesium stearate, and D&C Yellow No. 10 Aluminum Lake. Croscarmellose sodium promotes rapid capillary water wicking into the tablet core.
- Mallinckrodt M367: Formulated with colloidal silicon dioxide, crospovidone, microcrystalline cellulose, povidone, pregelatinized starch, and stearic acid. Crospovidone provides rapid effervescent-like swelling in gastric acid.
03. Dissolution curves: The 15-minute gastric breakdown profile
In USP in-vitro paddle dissolution tests using simulated gastric fluid (0.1N HCl at 37°C), both Watson 853 and Mallinckrodt M367 release over 85% of their active hydrocodone and acetaminophen content within 15 minutes. This rapid dissolution profile ensures that the onset of pain relief is clinically indistinguishable between the two tablets in acute clinical settings.
04. The psychology of pill color: Why some patients swear by “the yellow ones”
In clinical pain management, patients frequently express a strong preference for yellow Watson 853 tablets over white M367 pills, claiming that the yellow tablets provide stronger pain relief. Psychopharmacological research confirms that this is driven by color-associated psychological priming: vibrant colors (yellow, red, orange) are unconsciously perceived by human brains as more potent and energizing than plain white tablets. In double-blind clinical trials where tablets were placed inside identical opaque gelatin capsules, patients could not distinguish between Watson and Mallinckrodt.
05. Manufacturer consistency recommendations
While Watson 853 and Mallinckrodt M367 are therapeutically bioequivalent, patients recovering from complex orthopedic surgeries or managing acute trauma should ask their dispensing pharmacy to maintain the same manufacturer on refills if possible. Consistency avoids unnecessary psychological distress and provides predictable day-to-day pain management.
06. Detailed Receptor Neurobiology, CYP2D6 Hydromorphone Bioactivation & APAP Synergy
At the molecular and clinical level, Hydrocodone / APAP combines two distinct, synergistic analgesic compounds designed to attack nociceptive signaling through dual central and peripheral mechanisms:
1. Hydrocodone Component: Hydrocodone is a semi-synthetic phenanthrene opioid agonist that binds selectively to the μ-opioid receptor (MOR) on primary afferent neurons in the dorsal horn substantia gelatinosa and brainstem periaqueductal gray (PAG). Receptor coupling to inhibitory Gi/o proteins inhibits adenylyl cyclase, closes N-type voltage-gated calcium channels, and stimulates inward-rectifying potassium channels. This hyperpolarizes neuronal membranes, dramatically inhibiting presynaptic release of substance P, glutamate, and neurokinins.
Furthermore, hydrocodone undergoes critical hepatic O-demethylation catalyzed by cytochrome P450 2D6 (CYP2D6) into hydromorphone. Hydromorphone exhibits a 6- to 10-fold higher binding affinity for μ-opioid receptors than parent hydrocodone, contributing significantly to clinical analgesia. Patients who are CYP2D6 poor metabolizers experience diminished pain relief, whereas ultra-rapid metabolizers risk exaggerated sedation and respiratory depression.
2. Acetaminophen (APAP) Component: Acetaminophen produces analgesia primarily through central inhibition of cyclooxygenase (COX-1, COX-2, and putative central COX-3/peroxidase variants) and modulation of endogenous cannabinoid and descending serotonergic inhibitory pathways. Unlike NSAIDs, APAP lacks peripheral anti-inflammatory effects and does not cause gastric ulceration or platelet inhibition.
| PHARMACOLOGICAL AGENT | PRIMARY MOLECULAR TARGET | HEPATIC METABOLIC ENZYME | CLINICAL ANALGESIC ROLE | CRITICAL CLINICAL HAZARD |
|---|---|---|---|---|
| Hydrocodone | μ-Opioid Receptor (MOR) Agonism | CYP2D6 (to Hydromorphone) & CYP3A4 (to Norhydrocodone) | Blocks ascending nociceptive pain signaling in spinal cord | Respiratory depression, physical dependence, constipation |
| Acetaminophen (APAP) | Central COX / Peroxidase Site Inhibition | Glucuronidation (55%), Sulfation (30%), CYP2E1 (to NAPQI) | Synergistic pain threshold elevation; opioid-sparing effect | Hepatotoxicity / Centrilobular necrosis at >4,000mg/day |
| Hydromorphone (Metabolite) | High-Affinity μ-Opioid Agonist (Ki ~0.37 nM) | Phase II Glucuronidation via UGT2B7 | Potent amplification of central analgesic efficacy | Toxicity in CYP2D6 ultra-rapid metabolizers |
| NAPQI (Reactive Metabolite) | Hepatocyte macromolecules | Detoxified by intracellular glutathione (GSH) | None (Toxic intermediate) | Glutathione depletion leads to irreversible liver failure |
The combination of hydrocodone with acetaminophen creates potent therapeutic synergy, enabling lower doses of the opioid component while maximizing relief for moderate to severe acute musculoskeletal and post-surgical pain.
07. Hepatic Clearance, Renal Impairment & Beers Criteria Safety
Pharmacokinetic clearance of Hydrocodone / APAP involves dual metabolic pathways for both hydrocodone and acetaminophen, requiring strict clinician oversight across specific organ impairment subgroups:
| PATIENT POPULATION | PHARMACOKINETIC KINETICS | DOSING MODIFICATION DIRECTIVE | CRITICAL CLINICAL MANDATE |
|---|---|---|---|
| Hepatic Impairment (Mild-Moderate) | Impaired APAP glucuronidation and reduced hydrocodone clearance | Cap APAP ≤2,000mg / 24 hours; extend dosing intervals to Q8H-Q12H | Monitor transaminases; avoid in acute hepatitis or liver decompensation |
| Severe Hepatic Cirrhosis (Child-Pugh C) | Glutathione depletion; severe hydrocodone metabolic shunting | CONTRAINDICATED: Extreme hepatotoxicity & encephalopathy risk | NAPQI accumulation precipitates fatal hepatic centrilobular necrosis |
| CYP2D6 Poor Metabolizers (~7% Caucasians) | Minimal conversion of hydrocodone to active hydromorphone | Evaluate alternative analgesics; do not dangerously escalate dose | Escalating doses causes toxic hydrocodone/APAP buildup without pain relief |
| CYP2D6 Ultra-Rapid Metabolizers | Rapid, massive bioactivation into hydromorphone | Initiate at 50% standard starting dose; monitor breathing | High risk of sudden, life-threatening respiratory depression |
| Renal Impairment (CrCl < 30 mL/min) | Prolonged hydrocodone elimination half-life; APAP metabolite retention | Increase dosing intervals to every 8 to 12 hours | Monitor for severe cognitive blunting and respiratory depression |
| Geriatric Patients (≥ 65 Years) | Decreased hepatic mass, diminished renal clearance, CNS sensitivity | Start at lowest manufactured dose (e.g. 5/325mg); Beers Criteria oversight | Proactive bowel management mandatory to prevent severe fecal impaction |
Absolute Daily Acetaminophen (APAP) Ceiling: Under FDA regulations, the total cumulative daily dose of acetaminophen from all sources combined (including OTC cough/cold elixirs, sinus remedies, and headache pills) must never exceed 4,000mg per 24 hours. For chronic or elderly patients, clinicians recommend a safer conservative threshold of 3,000mg daily (or ≤2,000mg in chronic alcohol consumers) to protect hepatic glutathione reserves.
08. Comprehensive Patient Clinical Safety & Dispensing Checklist
Before initiating therapy or taking each scheduled dose of Hydrocodone / APAP, patients, caregivers, and clinical teams must review this standardized clinical verification checklist to prevent life-threatening adverse drug events and fatal toxicities:
PATIENT PRE-ADMINISTRATION SAFETY CRITERIA
- Total Acetaminophen (APAP) Audit: Verify that the patient is not taking ANY other products containing acetaminophen (e.g., Tylenol, DayQuil, NyQuil, Excedrin, Percocet). Total APAP from all sources must never exceed 4,000mg/day (clinically target ≤3,000mg/day).
- Absolute Alcohol Prohibition: Strict zero-tolerance for alcohol. Ethanol massively accelerates liver glutathione depletion (triggering acute liver failure from APAP) while paralyzing brainstem respiratory drive alongside hydrocodone.
- Concurrent Benzodiazepine & Sedative Screen: Check for co-prescribed anti-anxiety drugs (alprazolam, diazepam, lorazepam) or sleep aids. The FDA Boxed Warning strictly advises against co-prescribing without active emergency naloxone on site.
- Emergency Naloxone (Narcan) Access: Ensure household members or caregivers know the location of emergency naloxone nasal spray and how to administer it in case of accidental overdose or respiratory collapse.
- Proactive Bowel Regimen Initiation: Opioids inevitably cause opioid-induced constipation (OIC) by paralyzing gastrointestinal motility. Daily fluid intake, dietary fiber, and scheduled osmotic or stimulant laxatives (senna, PEG 3350) should begin with the very first dose.
- Locked Storage & Disposal Safeguards: Store securely in a locked lockbox out of sight and reach of children, visitors, and pets. Accidental single-tablet ingestion of 10mg hydrocodone can cause fatal respiratory arrest in a toddler.
09. Verified Pharmaceutical Formulations & Prescribing Profiles
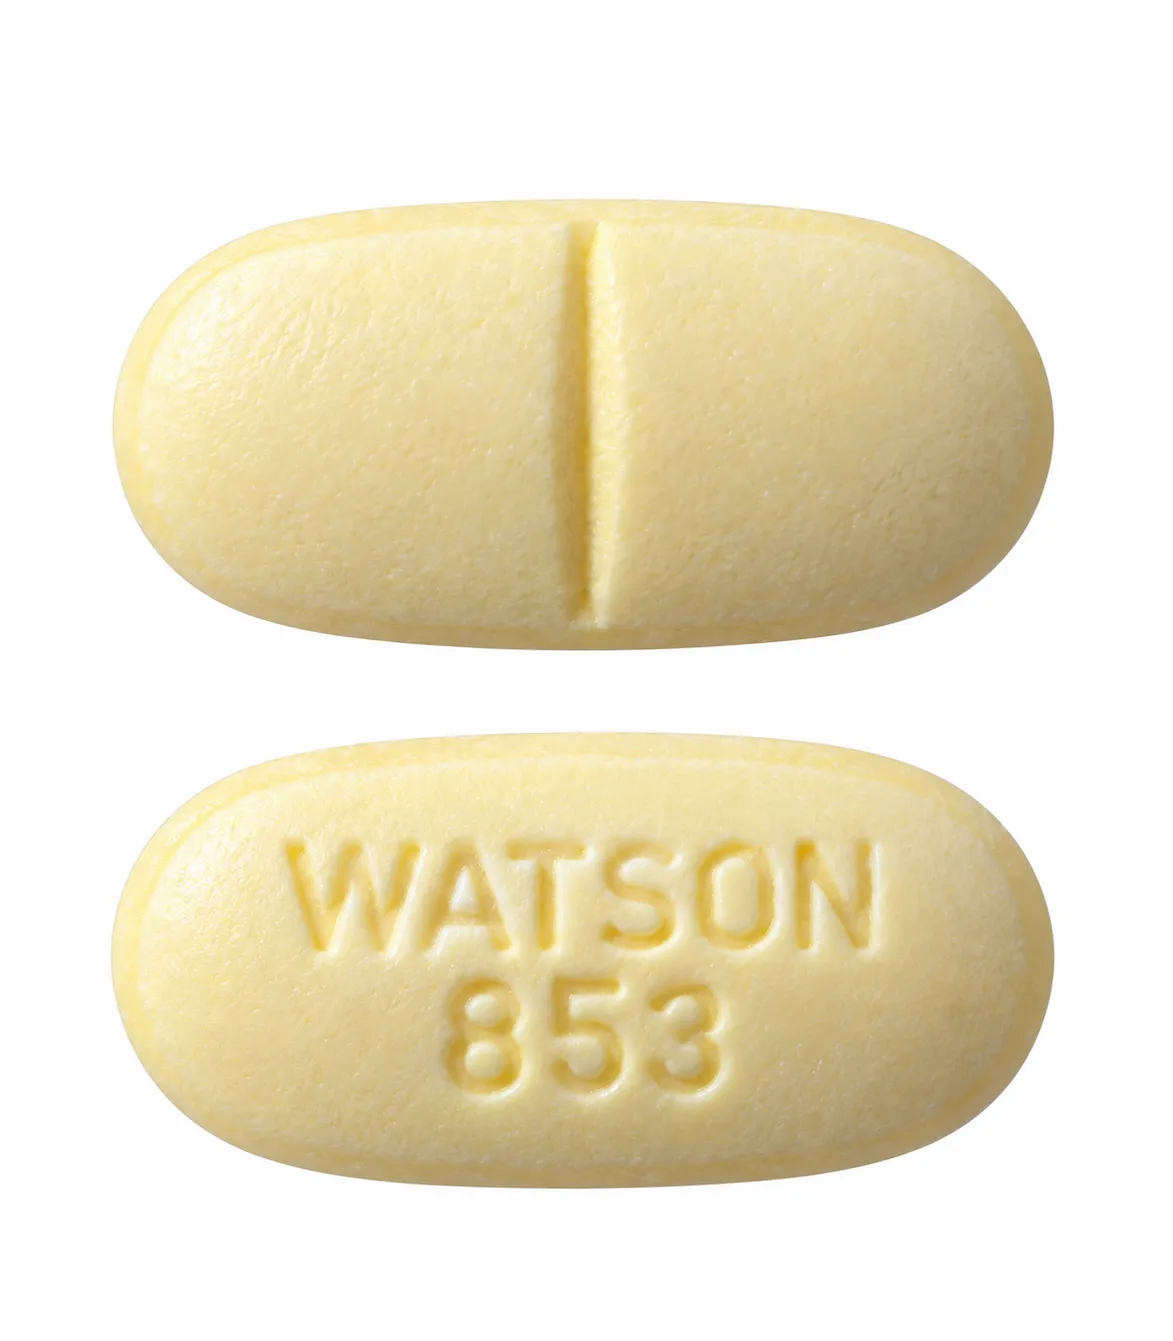
Hydro Watson (Hydrocodone / APAP 10/325mg)
Watson 853 yellow oblong oral tablets indicated for moderate to severe acute musculoskeletal pain.
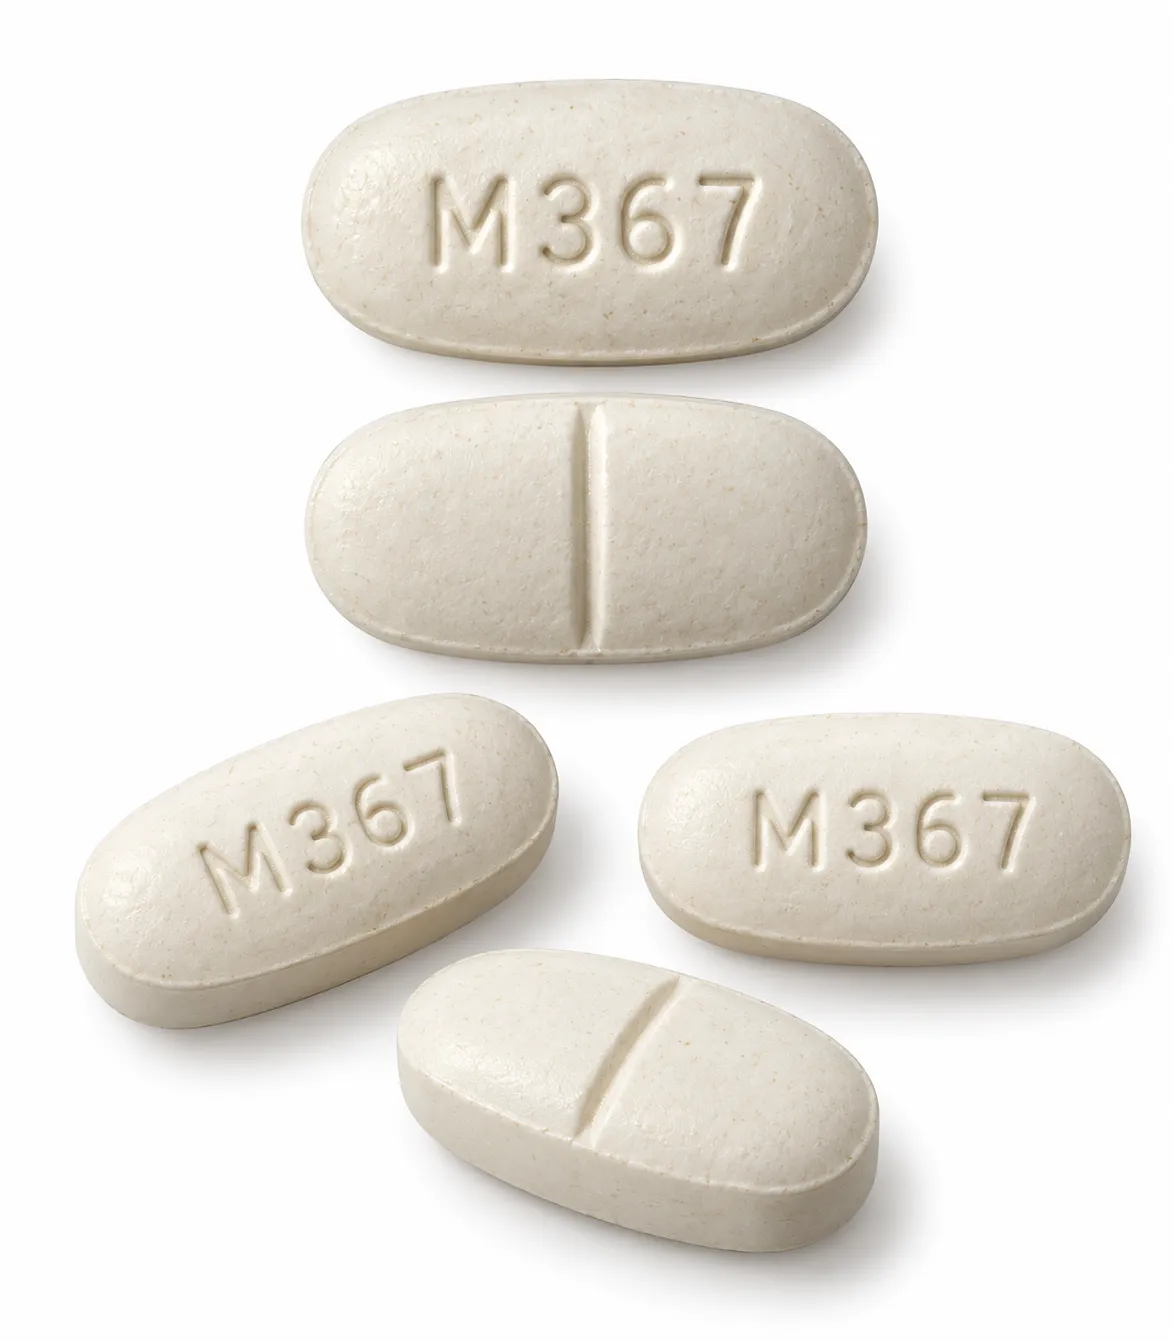
Hydro M367 (Hydrocodone / APAP 10/325mg)
Mallinckrodt M367 white capsule-shaped tablets engineered for consistent dual-action analgesia.
10. Frequently Asked Questions
Are yellow Watson 853 pills better than white M367 pills?
Clinically, no. Both pills contain the exact same amount of hydrocodone (10mg) and acetaminophen (325mg) and are proven to absorb into the body at the identical rate. Some patients prefer the yellow pill due to psychological color perception.
Do Watson 853 and M367 have the same side effects?
Yes. Because the active medications are identical, both cause the same potential side effects: drowsiness, dizziness, nausea, and constipation.
Can a pharmacy substitute M367 for Watson 853?
Yes. Because both are FDA-rated “AB equivalent” generic equivalents, pharmacies can legally substitute one for the other depending on wholesale stock availability.
Why are Watson 853 pills yellow?
Watson adds an approved food-grade yellow dye (D&C Yellow No. 10) to make their pills visually distinctive from other pain medications and brand strengths.
11. Clinical References & Regulatory Sources
- FDA CDER. Approved Drug Products with Therapeutic Equivalence Evaluations (Orange Book). Source Database.
- Clinical Pharmacokinetics. Bioequivalence and dissolution kinetics of generic hydrocodone/acetaminophen formulations. Source Database.
- The Journal of Clinical Pharmacology. Impact of tablet color and shape on patient expectation and perceived analgesic potency. Source Database.
Consult a Clinical Pharmacy Specialist
Have questions regarding Hydrocodone / APAP dosing intervals, CYP enzyme interactions, or physician-guided discontinuation protocols? Connect with our licensed clinical pharmacy team for patient safety guidance.
Related Patient Services & Verified Care
Every prescription order is verified by a licensed pharmacist in strict adherence to FDA BeSafeRx protocols.