
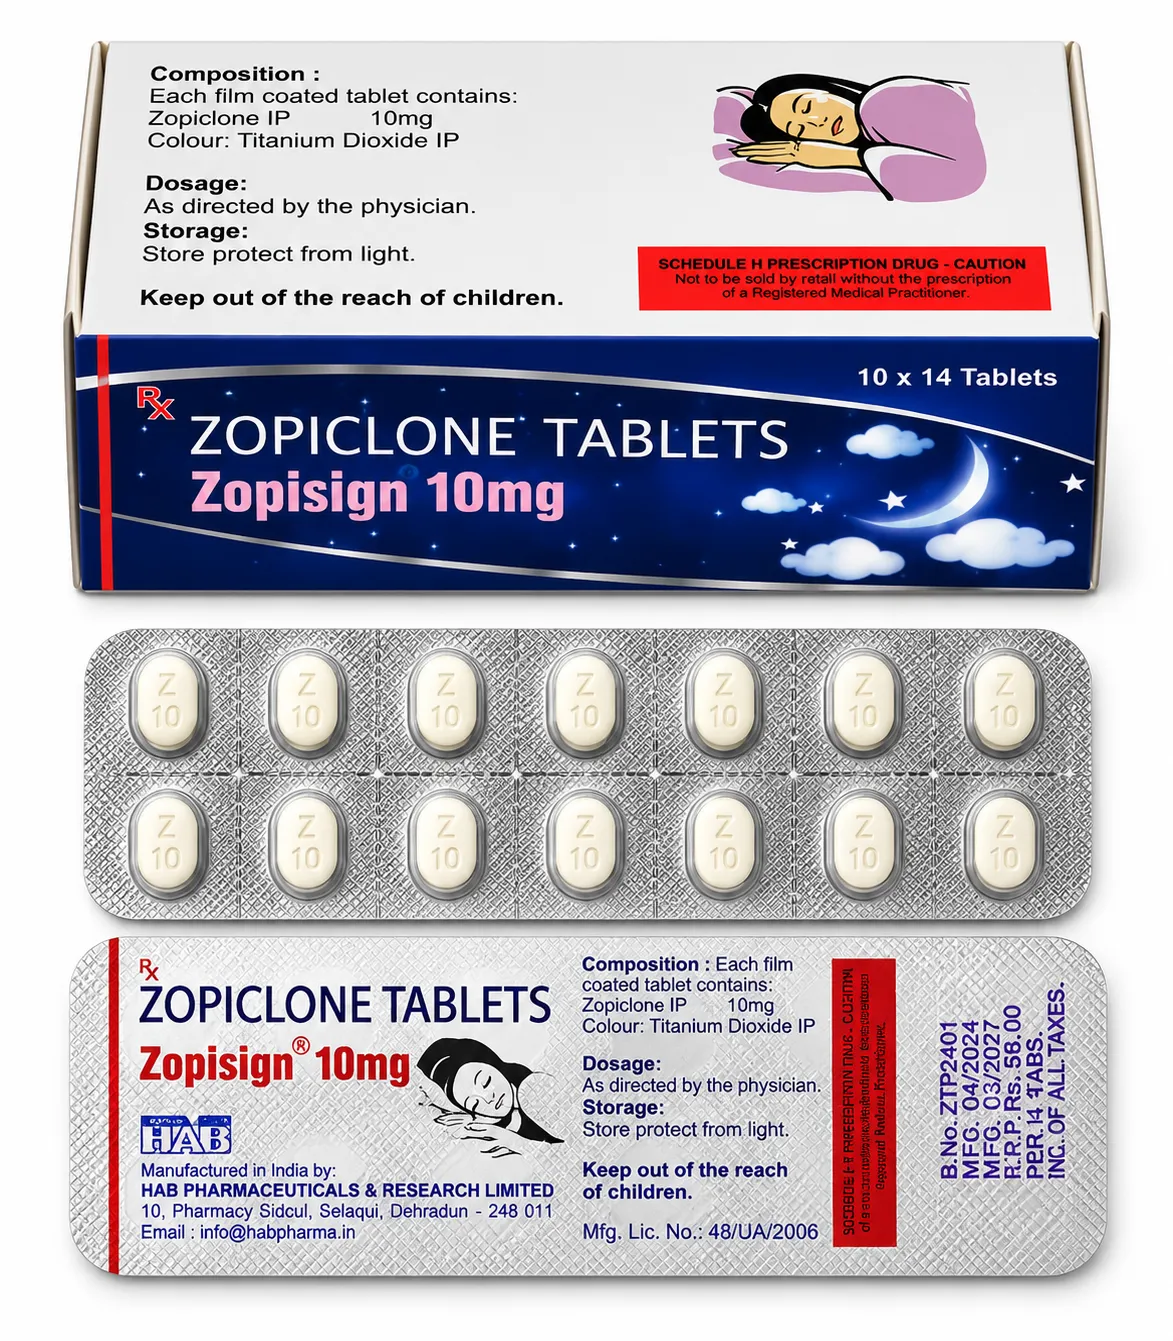
Zopiclone Side Effects: Bitter Metallic Taste (Dysgeusia), Complex Sleep Behaviors (Parasomnias), and Next-Day Impairment

Zopiclone Side Effects: Bitter Metallic Taste (Dysgeusia), Complex Sleep Behaviors (Parasomnias), and Next-Day Impairment
A comprehensive clinical safety review of zopiclone adverse events, salivary excretion dysgeusia, sleep-walking parasomnias, and driving safety.
CLINICAL SAFETY REVIEW
EXECUTIVE CLINICAL SUMMARY
Zopiclone (Zopisign® / Imovane®) is an effective cyclopyrrolone hypnotic, but its therapeutic administration is accompanied by unique, class-defining adverse effects. The most universally recognized side effect is a bitter or metallic taste (dysgeusia)—occurring in up to 30% of patients—caused by active drug secretion into human saliva. In addition, next-morning somnolence, dry mouth, dizziness, and anterograde amnesia are common complaints. Most critically, zopiclone carries stringent regulatory warnings regarding complex sleep behaviors (parasomnias)—including sleep-walking, preparing and eating food while asleep, making phone calls, and sleep-driving with zero conscious memory. Understanding these risks is vital for patient safety and accident prevention.
01. Clinical trial incidence and physiological drivers of adverse events
In controlled clinical trials across adult and elderly insomnia cohorts, adverse events predominantly reflect central GABA-A receptor modulation and systemic pharmacokinetic distribution.
| ADVERSE EVENT | INCIDENCE (ZOPICLONE 7.5mg – 10mg) | INCIDENCE (PLACEBO) | PHYSIOLOGICAL MECHANISM | CLINICAL ACTION |
|---|---|---|---|---|
| Bitter / Metallic Taste (Dysgeusia) | 25% – 30% | 1% – 2% | Active secretion of parent zopiclone into salivary secretions | Harmless; rinse mouth with lemon water; chew citrus gum |
| Dry Mouth (Xerostomia) | 8% – 12% | 3% | Mild anticholinergic/salivary fluid composition shift | Maintain bedside oral hydration with water |
| Next-Morning Somnolence / Hangover | 7% – 12% | 2% | Residual plasma concentration at 8h (t½ ~5 hours) | Ensure strict 7-8h sleep window; reduce dose to 5mg |
| Dizziness / Lightheadedness | 5% – 8% | 2% | Vestibular and brainstem reflex suppression | Rise slowly from bed; avoid walking in dimly lit rooms |
| Anterograde Amnesia | 3% – 5% | <1% | Hippocampal CA1 long-term potentiation blockade | Take tablet while already in bed; turn off all screens |
| Complex Sleep Behaviors (Parasomnias) | <1% – 2% | <0.5% | Thalamocortical motor disinhibition during NREM sleep | Discontinue immediately: Permanent contraindication |
02. The science of the bitter metallic taste (Dysgeusia)
A unique pharmacological hallmark of zopiclone is the bitter, metallic aftertaste that patients experience in the back of their throat upon waking. This is not caused by pill residue in the esophagus; rather, zopiclone is actively secreted from blood capillaries into the saliva of the parotid and submandibular salivary glands. Because the zopiclone molecule possesses a strong inherently bitter chemical moiety, its presence in saliva stimulates bitter taste receptors (TAS2Rs) on the circumvallate papillae of the tongue. While harmless, patients can mitigate this taste by drinking acidic citrus water, chewing peppermint gum, or using mild antibacterial mouthwash in the morning.
03. Complex sleep behaviors (Parasomnias): The black-box warning
Regulatory health agencies worldwide mandate a prominent warning regarding complex sleep behaviors. These are activities performed while the patient is fully asleep and unaroused, followed by complete retrograde amnesia the next morning:
- Sleep-Driving: Patients get into their automobiles and drive on public roads while in a hypnotic sleep state, leading to catastrophic vehicular collisions.
- Sleep-Cooking & Eating: Patients prepare elaborate meals on hot stovetops or consume non-edible items with extreme burn and fire risks.
- Nocturnal Communication: Sending nonsensical emails, text messages, or making phone calls without conscious awareness.
- Mandatory Action: If a patient reports even a single episode of complex sleep behavior, zopiclone must be discontinued immediately and permanently; rechallenge is strictly contraindicated.
04. Next-day psychomotor and driving impairment
Because zopiclone has an elimination half-life of 5 hours (longer than zolpidem), active drug levels can remain elevated 8 to 10 hours post-dose, particularly in women, elderly individuals, or patients taking 10mg doses. Simulated driving evaluations demonstrate significant lane-weaving, impaired peripheral hazard detection, and delayed braking latency. Patients must allow a full 8 hours between taking zopiclone and driving an automobile.
05. Geriatric fall risks: AGS Beers Criteria guidelines
Older adults (≥65 years) experience double the rate of nocturnal unsteadiness and balance loss on zopiclone. When seniors wake up during the night to use the bathroom, residual ataxia combined with dark hallways leads to catastrophic domestic falls, femoral neck fractures, and subdural hematomas. Bedside nightlights and non-slip rugs are essential safeguards.
06. Detailed Hypnotic Neurobiology, Selective α1 GABA-A Modulation & Sleep Architecture
At the molecular level, Zopiclone (zolpidem) is a non-benzodiazepine hypnotic belonging to the imidazopyridine chemical class. Unlike classical benzodiazepines that bind non-selectively across all α1, α2, α3, and α5 subunit-containing GABA-A receptors, zolpidem exhibits high preferential affinity and positive allosteric selectivity for the α1 subunit-containing GABA-A receptor complex (classically designated the benzodiazepine-1 or BZ1 receptor subtype).
The α1 subunit is localized primarily in the cerebral cortex, substantia nigra, and sensorimotor relay nuclei of the thalamus—regions responsible for regulating vigilance, cortical arousal, and sleep latency. By selectively augmenting GABA-stimulated chloride conductance at α1 complexes, zolpidem rapidly induces hypnotic slumber while producing significantly less muscle relaxation, anxiolysis, or anticonvulsant activity compared to non-selective agents.
| GABA-A SUBUNIT ISOFORM | ZOLPIDEM BINDING AFFINITY | NEUROANATOMICAL DISTRIBUTION | PRIMARY CLINICAL EFFECT |
|---|---|---|---|
| α1 Subunit (BZ1) | High Affinity (Ki ~19 nM) | Cerebral cortex, thalamus, substantia nigra | Rapid sleep latency reduction, hypnotic induction, slow-wave sleep |
| α2 Subunit (BZ2) | Low Affinity (Ki >180 nM) | Limbic system, amygdala, striatum | Minimal daytime anxiolysis at standard hypnotic doses |
| α3 Subunit (BZ2) | Low Affinity (Ki >250 nM) | Spinal interneurons, reticular formation | Negligible peripheral muscle relaxation |
| α5 Subunit (BZ3) | Negligible Affinity (Ki >1,000 nM) | Hippocampus, temporal lobe memory circuits | Preserved temporal memory formation outside peak sedation |
Polysomnographic sleep architecture studies demonstrate that zolpidem preserves physiological sleep stages, maintaining Stage 3 and Stage 4 deep slow-wave sleep and exerting minimal disruptive impact on rapid eye movement (REM) sleep when administered at recommended therapeutic doses.
07. Hepatic Clearance, Renal Impairment & Beers Criteria Safety
Clinical dosing of Zopiclone requires strict gender-specific and hepatic impairment adjustments due to substantial clearance differences:
| PATIENT SUBGROUP | CLEARANCE KINETICS & AUC | FDA RECOMMENDED DOSING | CLINICAL SAFETY MANDATE |
|---|---|---|---|
| Adult Females | 45% lower oral clearance than males (higher morning Cmax) | 5mg immediately before bedtime | Reduces next-morning driving impairment |
| Adult Males | Standard oxidative hepatic clearance via CYP3A4 | 5mg to 10mg immediately before bedtime | Do not exceed 10mg; allocate 7-8 hours sleep |
| Geriatric Patients (≥ 65 Years) | Prolonged elimination half-life (~3.0 to 4.0 hours) | 5mg immediately before bedtime maximum | Beers Criteria warning: fall risk and nocturnal confusion |
| Hepatic Impairment (Child-Pugh A/B) | 5-fold increase in AUC, Cmax doubles | 5mg maximum; avoid in severe cirrhosis | Contraindicated in severe hepatic failure |
Under FDA black-box warnings and AGS Beers Criteria®, sedative-hypnotics must be prescribed at the lowest effective dose for the shortest possible duration (typically ≤7 to 10 days) to prevent physical dependence, tolerance, and nocturnal confusion.
08. Comprehensive Patient Clinical Safety & Dispensing Checklist
Before administering Zopiclone, patients and caregivers must verify this pre-dose safety checklist to prevent dangerous sleep-state emergencies:
PRE-BEDTIME CLINICAL SAFETY CRITERIA
- Bedside Timing Rule: Ingest tablet immediately prior to getting into bed—never 30 or 60 minutes beforehand while walking around the home.
- 7 to 8-Hour Dedicated Sleep Window: Only take zolpidem if you have at least 7 to 8 full hours to dedicate to uninterrupted sleep before waking.
- Complex Sleep Behavior Warning: Discontinue immediately if sleep-walking, sleep-driving, preparing food while asleep, or making phone calls without memory occurs.
- Alcohol & CNS Depressant Ban: Zero alcohol consumption on the evening of administration; never combine with opioids or tranquilizers.
- Empty Stomach Administration: Take on an empty stomach; food delays sleep onset and lowers peak therapeutic levels.
09. Verified Pharmaceutical Formulations & Prescribing Profiles
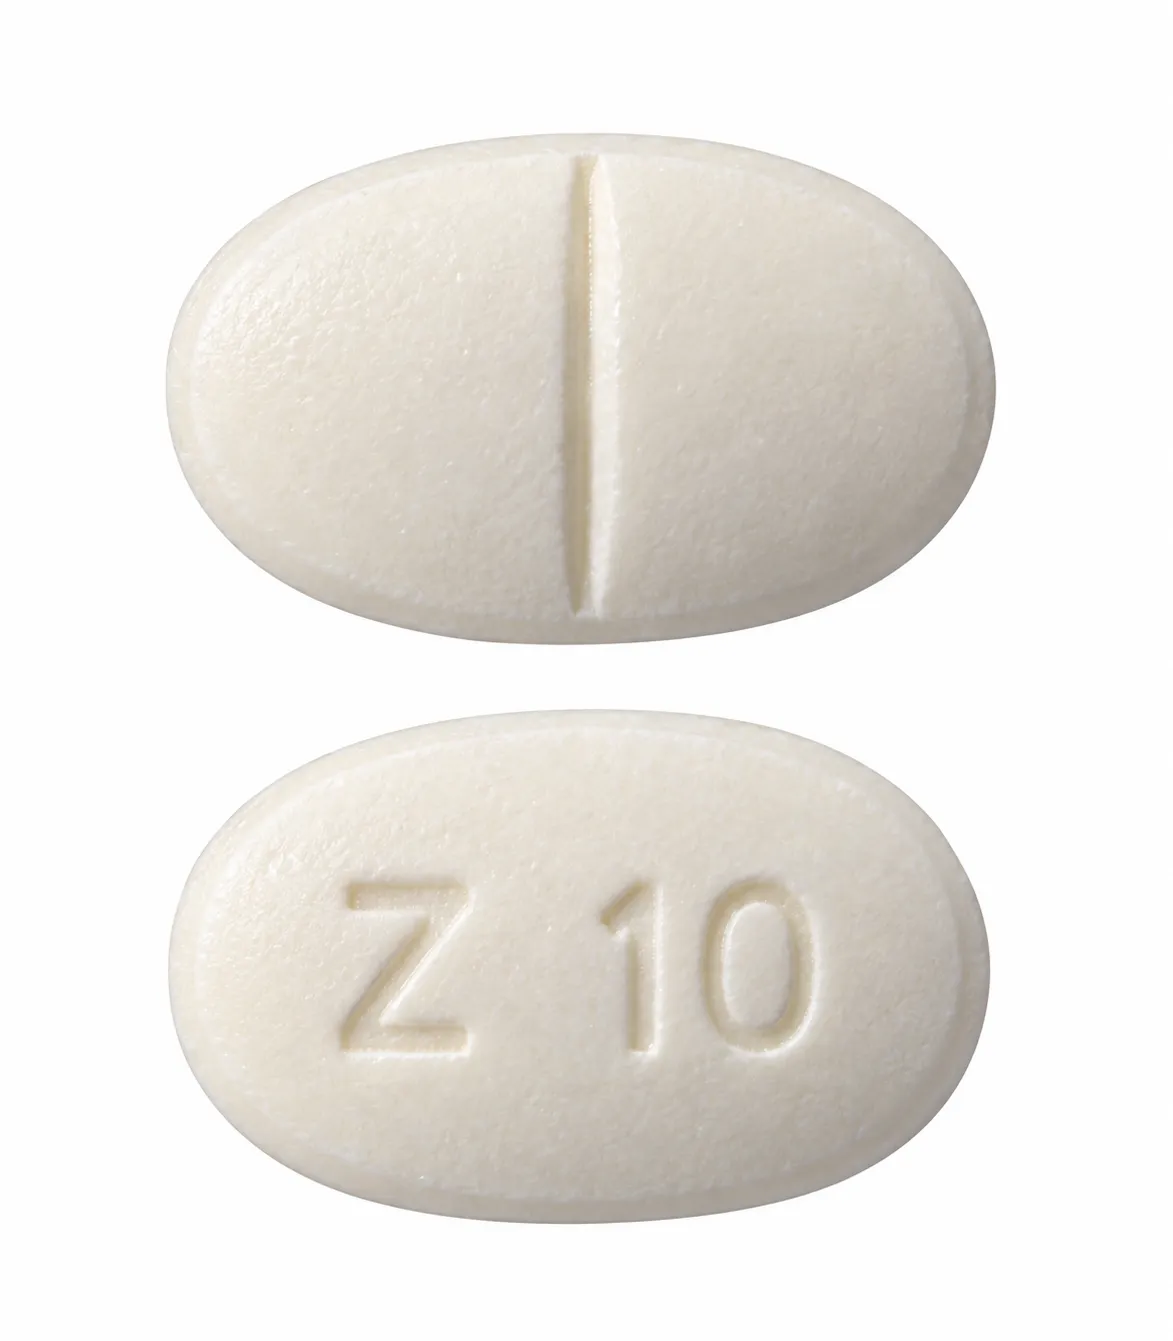
Zopiclone 10mg (Zopisign)
First-line non-benzodiazepine hypnotic engineered for severe sleep-onset and sleep-maintenance insomnia with minimal residual morning sedation.
10. Frequently Asked Questions
Why does zopiclone 10mg make everything taste bitter or metallic?
The bitter metallic taste is caused by the medicine passing naturally from your bloodstream into your saliva. It is completely harmless, occurs in about 1 out of 3 people, and usually fades by mid-day.
What should I do to get rid of the metallic taste from zopiclone?
Brushing your teeth, rinsing with an alcohol-free mouthwash, drinking lemon water, or chewing citrus or peppermint gum in the morning helps mask the taste.
What are complex sleep behaviors, and why are they dangerous?
Complex sleep behaviors occur when someone walks, eats, makes phone calls, or even drives a car while completely asleep after taking a sleeping pill. If this happens, you must stop taking zopiclone immediately and call your doctor.
Is it safe to drive to work the morning after taking zopiclone 10mg?
Yes, but only if you had at least 8 full hours of sleep. If you wake up feeling dizzy, sluggish, or groggy, you should not drive until the grogginess clears.
11. Clinical References & Regulatory Sources
- EMA. European Medicines Agency Pharmacovigilance Risk Assessment Committee (PRAC): Z-Drugs and Complex Sleep Behaviors. Source Database.
- British Journal of Clinical Pharmacology. Salivary excretion of zopiclone and mechanisms of metallic taste dysgeusia. Source Database.
- Sleep Medicine Reviews. Risk of falls and hip fractures associated with hypnotic z-drugs in elderly cohorts. Source Database.
Consult a Clinical Pharmacy Specialist
Have questions regarding Zopiclone dosing intervals, CYP enzyme interactions, or physician-guided discontinuation protocols? Connect with our licensed clinical pharmacy team for patient safety guidance.
Related Patient Services & Verified Care
Every prescription order is verified by a licensed pharmacist in strict adherence to FDA BeSafeRx protocols.